Our Work

  • Reset Filters
  • Topic Areas

  • Content Types

  • Authors / Speakers

  • Reset Filters

1377 Results

Pharmaceutical Industry Pay-Per-Click Advertising Strategies to Influence Public Opinions on Drug Pricing

Eisenkraft Klein D, Kesselheim AS - Clinical Pharmacology & Therapeutics

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

How Congress Can Fix Expert Advisory Committees

Daval CJR, Kesselheim AS - STAT

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.

Methodological Divergence in Oncology HTA: Implications for International Harmonization and the Handling of Uncertainty

Chen NC, Bullement A, Zemplenyi AT, O'Bryant CL, Kaizer AM, Anderson KE, McQueen RB - PharmacoEconomics Open

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

Coverage and Costs for Medications After Medicare Price Negotiation

Cai CL, Bucha S, Kesselheim AS, Rome BN - Journal of General Internal Medicine

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

International Regulatory Status and Reimbursement Recommendations of Haematological Malignancy Drugs Withdrawn from the FDA Accelerated Approval Pathway

Mulsant SS, Kesselheim AS, Naci H - Journal of Cancer Policy

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

The Impact of Semantics in Medicines Regulation

Costa E, Kesselheim AS - Journal of Law, Medicine, & Ethics

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.

Politics and the Patient Encounter, in Dire Times

Avorn J - MedPage Today

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.

Comments on FDA Discussion Paper, “Considerations for the Regulation of Generative AI-Enabled Medical Devices”

Jaiswal N, Gorijavolu R, Thomas S, Hwang TJ, Celi LA, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Comments on Reauthorization of the Generic Drug User Fee Amendments FY2028-2032 (GDUFA IV)

Martin MJ, Hwang TJ, Kesseheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Comments on Reauthorization of the Prescription Drug User Fee Act FY2028-2032 (PDUFA VIII)

Martin MJ, Hwang TJ, Tibau A, Rand LZ, Tanveer S, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Should Medicine and Public Health Abandon the Opioid Industry’s Terminology Surrounding Pain? An Argument for Conceptual Reclamation and Against Guilt-By-Provenance

Eisenkraft Klein D - Journal of Law, Medicine, & Ethics

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.

How Do Stakeholders Perceive Canada’s Drug Pricing Reforms? An Analysis of Submissions to Canada’s Patented Medicine Prices Review Board

Eisenkraft Klein D, Nicolson S, Kesselheim AS - International Journal of Health Policy and Management

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

The Legal Battle Over Mifepristone and the Future of FDA Regulation

Tu SS, Grossman LA, Feldman WB - Annals of Internal Medicine

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.

Comments on the Regulatory Alignment for Predictable and Immediate Device (RAPID) Coverage Pathway

Hwang TJ, Bucha S - Centers for Medicare and Medicaid Services (CMS)

  • Price, Value, and Access
  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Changes in Point-of-Sale Drug Prices After Medicare Eliminated Retroactive Pharmacy Fees

Rome BN, Cai CL, Gibbons JB, Kesselheim AS, Anderson KE - JAMA Network Open

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

Modifiable Drivers of Community Pharmacy Closures in Colorado and Utah: A Qualitative Focus Group Study

DiStefano MJ, Chen NC, Asche CV, Anderson KE, Mattingly TJ - Health Affairs Scholar

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

Supplemental Rebates from Drug Makers to State Medicaid Programs Grew Fivefold from 2017 to 2024

Yates MC, Gibbons JB, Kesselheim AS, Rome BN - Health Affairs

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

Comments in Response to Request for Information, “Considerations for Potential Future Therapeutic Use of Psychedelic Drugs”

Eisenkraft Klein D, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Delisted Patents on Pharmaceuticals, 1998-2024

Kirby-Rivera L, Feldman WB, Kim M, Kosmopoulou G, Kesselheim AS, Tu SS - Journal of Law, Medicine, & Ethics

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.

Prescription Drug Launch Price Trends Before and After the Inflation Reduction Act

Shanmugam H, Kesselheim AS, McGuire M, Rome BN - JAMA

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Launch prices for new prescription drugs increased by 8% per year from 2008 to 2025, with a median price over $250,000 for drugs approved in 2020-2025. There was no change in these trends after Congress passed the Inflation Reduction Act in 2022. More policies are needed to protect patients from rising launch prices, such as allowing Medicare to negotiate prices sooner after launch and expanding negotiated prices to patients with private insurance.
View Source

Delays in Access to Generic Semaglutide Point to Key Missing Pieces in Canada’s Drug Approval System

Eisenkraft Klein D, Kesselheim AS - Health Policy

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Canada approved its first generic semaglutide nearly four months after market exclusivity expired, with delays arising from the absence of clear standards for demonstrating equivalence between fully synthetic generics and the brand-name product. Regulators should publish equivalence standards so manufacturers can build the required evidence into their initial submissions, helping lower-cost alternatives reach patients sooner.
View Source

Recent Congressional Proposals To Promote Biosimilar Competition

Bonis T, Tu SS - Health Affairs Forefront

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Biologics account for more than half of US drug spending, yet US biosimilar uptake is about half that of the European Union. Three bipartisan bills could improve competition: the Biosimilar Red Tape Elimination Act would make all biosimilars interchangeable, the ETHIC Act would limit patent thickets and serial litigation, and the MAPI Act would require patent applicants to share relevant FDA information with the USPTO.
View Source

Post-Hearing Comments on the Section 301 Investigation of Germany’s Persistent Underpayment for Innovative Pharmaceutical Products

Hwang TJ - Office of the US Trade Representative (USTR)

  • Price, Value, and Access
An icon of a bill representing government policy.

Patient Participation and the Power of Persuasion: A Qualitative Analysis of Patient Testimonies During FDA Drug Advisory Committees

Eisenkraft Klein D, Mooney H, Bhaskar A, McCabe J, Kesselheim AS, Rome BN, Rand LZ - Journal of Health Politics, Policy, and Law

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
This qualitative evaluation of 844 patient and family testimonials from 155 FDA advisory committee meetings from 2015 to 2023 found that speakers often follow a recurring structure: establishing credibility, describing the burden of illness, presenting treatment experiences as evidence, and appealing to regulators’ moral responsibilities. Many emphasized feeling overlooked by the health care system and linked FDA approval to patient autonomy. The findings raise questions about how patient testimony should inform regulatory decisions and how to optimize patient engagement in the regulatory process.
View Source

Patents on Small-Molecule Drugs Approved by the US Food and Drug Administration, 1990-2019

Tu SS, Freeman N, Teng TW, Feldman WB, Kesselheim AS, Parton J, Wouters OJ - JAMA

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among nearly 2,000 small-molecule drugs approved by the FDA from 1990 to 2019, the mean number of patents listed in the Orange Book rose from 2.1 to 6.9 per drug. Nonprimary patents on formulations, methods of use, and delivery devices accounted for 84% of listed patents, 87% of those litigated against generic manufacturers, and 96% of those issued after FDA approval. The gap between a drug’s first- and last-to-expire patents also grew from a mean of 2.0 years to 6.1 years during this period. Limiting the number of continuation patents that can be asserted in litigation and increasing USPTO scrutiny of post-approval patents may be needed to ensure timely generic competition.
View Source

Letter: Setting the Record Straight on Terminal Disclaimers and the ETHIC Act

Kesselheim AS, Tu SS, Chao B, Lemley MA, Sarpatwari A, Carrier MA - 119th Congress, House Committee on the Judiciary, Subcommittee on Courts, Intellectual Property, Artificial Intelligence, and the Internet

  • Innovation Incentives and Competition
An icon of a bill representing government policy.

Testimony: The Evidence Does Not Support A Positive Determination in the Section 301 Investigation of Germany’s Pharmaceutical Policies

Hwang TJ - Office of the US Trade Representative (USTR)

  • Price, Value, and Access
An icon of a bill representing government policy.

Comments on Draft Guidance, “Demonstrating Substantial Evidence of Effectiveness for Human Drug and Biological Products”

Tibau A, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Improving Transparency of Drug Regulatory Decisions

Siebert M, Tibau A - BMJ

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Drug authorization is often presented as a unanimous decision, even when regulatory experts disagree about a medicine’s benefits, risks, and evidentiary uncertainties. Regulators should make scientific dissent more visible by reporting disagreements and voting outcomes. Greater transparency would help patients, clinicians, and policymakers understand regulatory uncertainty, see whether concerns are addressed over time, and strengthen public trust.
View Source

Brief of Public Health and Health Law Scholars in Commonwealth of Massachusetts v. Trump

Kesselheim AS - US District Court for the District of Massachusetts

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

Physician Understanding and Perceptions of Risk Communication Related to Drugs Covered by Risk Evaluation and Mitigation Strategy Programs

Zakoul H, Cosenza C, Lee SB, Tekle W, Freedman A, Belitkar S, Toyserkani GA, Oswell KH, LaCivita C, Dal Pan GJ, Kesselheim AS, Sarpatwari A - Pharmacoepidemiology and Drug Safety

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In semi-structured interviews with 50 physicians, most were aware of FDA Risk Evaluation and Mitigation Strategy (REMS) testing requirements for drugs and viewed REMS programs as valuable sources of risk communication. To improve implementation of these programs, physicians reported wanting more information on managing side effects, more accessible information on REMS requirements, integration of REMS programs with electronic medical records, and more timely updates to REMS materials as new safety data emerge.
View Source

Brief of 38 Intellectual Property Law Professors in Kahoot! AS v. Interstellar Inc.

Tu SS - US Supreme Court

  • Innovation Incentives and Competition
An icon of a bill representing government policy.

Most-Favoured-Nation Pricing for Prescription Drugs in US Medicare: A Cohort Study

Hwang TJ, Hediger S, Krishnan A, Cai CL, Kesselheim AS, Vokinger KN - Lancet

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Across 195 brand-name drugs, the most-favored-nation payment models for Medicare Part B (GLOBE) and Part D (GUARD) were estimated to yield net savings of $5.2 billion (16.1%) and $6.4 billion (17.6%), respectively, though savings would fall by more than 70% if manufacturers with separate agreements with HHS were exempted. For about three-quarters of drugs, projected Medicare savings exceeded the drug’s total annual sales in the lowest-priced reference country, suggesting manufacturers may be incentivized to delay launches or take other steps to avoid setting low reference prices abroad.
View Source

Patient Out-of-Pocket Spending on Generic and Brand-Name Prescription Drugs

Cai CL, Kesselheim AS, Rome BN - JAMA Network Open

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Policy efforts typically focus on improving affordability for brand-name medications, but this analysis of national survey data found that more than half of out-of-pocket spending by US patients is on generic drugs. Although generic medications are typically less expensive, they account for 90% of dispensed fills. More efforts may be warranted to improve the affordability of generic medications in the US.
View Source

Ban Bets on Unfinished Clinical Trials

Yang YT, Kesselheim AS - Science

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Prediction market contracts on whether ongoing late-stage clinical trials will meet their primary endpoints could undermine patient confidence, affect adherence, influence investigators’ assessment of subjective trial outcomes, and create strong incentives for insiders to leak confidential data. Financial exchanges, the Commodity Futures Trading Commission (CFTC), and Congress should prohibit such contracts until trials are complete and results are public, and trial sponsors should impose strict trading restrictions on investigators and vendors.
View Source

Pharmaceutical Products with Device-Only Patents: A Cross-Sectional Analysis

Feldman WB, Teng TW, Kotrannavar S, Tu SS - Nature Biotechnology

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Despite recent FTC enforcement, manufacturers continued to list “device-only” patents, which claim a product’s delivery device without mentioning its active ingredient, with the FDA for 55 products in 2026, including inhalers, intrauterine devices, and autoinjectors. The last-to-expire patents on 27 products (49%) were device-only, and these patents extended nominal protection by a median of 3.9 years beyond other patents. These findings highlight the potential impact of device patents on market competition for prescription drugs.
View Source

Budget Impact Analysis of Gene Therapies for Recessive Dystrophic Epidermolysis Bullosa

Raymakers AJN, Kesselheim AS, Feldman WB - JAMA Dermatology

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Although recessive dystrophic epidermolysis bullosa (RDEB) is an ultra-rare disease, two recently approved gene therapies for the condition could have large financial implications for US payers. The estimated budget impact of these therapies, beremagene geperpavec (B-VEC; Vyjuvek) and prademagene zamikeracel (PZ-CEL; Zevaskyn), was substantial across a range of uptake and utilization scenarios, highlighting the challenges high-cost gene therapies can create for health care budgets even when the eligible patient population is very small.
View Source

Limit Bets on Clinical-Trial Outcomes Being Placed on Prediction Markets

Hwang TJ, Gabriele SME - Nature

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Betting on clinical trial outcomes and regulatory decisions in US prediction markets could intensify financial pressure for misconduct by incentivizing exploitation of interim trial data and participants’ protected health information. Such bets could also bias how investigators grade outcomes and what participants report, and influence trial enrollment.
View Source

Industry Exposure in Medical Training: The Case for a Conflict-Free Learning Environment

Hauser JD, Kesselheim AS, Redberg R - Journal of Law, Medicine, & Ethics

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Conflict-of-interest reform in medical education has stalled over the past decade, even as industry payments to trainees continue to grow. To protect the integrity of physician training, medical schools and accrediting bodies should adopt and enforce stronger conflict-of-interest policies and include discussion of how funding sources can shape research in required curricula.
View Source

Comments for the Molecular and Clinical Genetics Panel of the Medical Devices Advisory Committee on the Galleri MCED Test

Tibau A, Hwang TJ, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.

PORTAL Post | September 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The September 2026 edition of the PORTAL Post monthly newsletter.
View Source

Esketamine Use and Attempted Suicide or Intentional Self-Harm Among Individuals with Treatment-Resistant Depression: A Retrospective Cohort Study

Wang Y, Storaci AS, Alexander GC, Gibbons JB - Drug Safety

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among over 23,000 adults with treatment-resistant depression (TRD) in a national claims database, esketamine (Spravato) use was not associated with a statistically distinguishable difference in nonfatal, medically attended suicide attempts or intentional self-harm.
View Source

Communicating Drug Safety and Safe Use Conditions in Risk Evaluation and Mitigation Strategy Materials

Sarpatwari A, Tessema FA, Mitra-Majumdar M, Lee SB, Zakoul H, Brown BL, Toyserkani GA, Oswell KH, LaCivita C, Dal Pan GJ, Woloshin S, Avorn J, Kesselheim AS - Drug Safety

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Educational materials for 13 drugs with Risk Evaluation and Mitigation Strategy (REMS) programs contained a median of 14 documents and 69 pages per program. Patient-directed materials had a median tenth-grade reading level, above the sixth-grade level recommended by the AMA, and took a median of 18 minutes per drug to read. REMS-specific risks appeared in a median of 80% of documents and drug indications in 33%, while drug benefits went unmentioned in 8 of 13 packages. Streamlining REMS materials for all audiences may improve comprehension and support safe use.
View Source

Comments on the 340B Drug Pricing Integrity and Affordability for Patients Act Discussion Draft

Feldman WB, Venkateswaran S, Martin MJ, Cai CL, Kesselheim AS - Office of Senator Bill Cassidy, 119th Congress

  • Price, Value, and Access
An icon of a bill representing government policy.
The commenters raise concerns that 340B Drug Pricing Integrity and Affordability for Patients Act’s proposed rebate-based model would give manufacturers expanded authority to withhold 340B discounts and could strain covered entities’ cash flow, while the bipartisan SUSTAIN 340B Act’s clearinghouse-based approach would be a more effective alternative. They also argue that proposed geographic restrictions on contract pharmacies are too narrowly drawn, and call for pairing 340B reform with broader measures to lower drug prices, including strengthening Medicare drug price negotiation and addressing pharmaceutical patent abuses.
View Source

Non-Approval in the Sunlight: FDA’s CRL Disclosures, the Limits of Confidentiality, and Lessons from the EMA

Lenarczyk G, Minssen T, Kesselheim AS - Journal of Law and the Biosciences

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
FDA’s 2025 disclosure of complete response letters (CRLs) represents a shift from historical treatment of CRLs as confidential, though the agency has not committed to a specific posting timeline for future disclosures. Drawing on a comparison with the European Medicines Agency’s more standardized disclosure practices, the authors recommend that FDA codify disclosure timelines and redaction standards, provide neutral summaries of CRLs when redactions obscure the basis for non-approval, and standardize the inclusion of prior-cycle CRLs in drug approval packages.
View Source

Realizing Benefits of First-in-Class Generic Entry—The Case of SGLT2 Inhibitors

Gondi S, Kesselheim AS, Rome BN - Clinical Pharmacology & Therapeutics

  • Innovation Incentives and Competition
  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Dapagliflozin (Farxiga) became the first SGLT2 inhibitor to face generic competition in 2026, but the savings may be limited if patients and clinicians continue to use empagliflozin (Jardiance), another SGLT2 inhibitor that remains patent protected. The authors offer strategies for patients, clinicians, and payers to maximize savings from first-in-class generic competition in the case of dapagliflozin and similar future cases.
View Source

Comments on the Expedited Investigational New Drug Pilot Program

Shah KM, Hwang TJ, Cliff ERS, Tibau A, Martin MJ, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
FDA should require robust conflict-of-interest safeguards, clear eligibility criteria for participating institutions, sponsors, and trials, and measures to protect patient safety before implementing its proposed Expedited Investigational New Drug (IND) Pilot Program, which would allow a small number of third-party “Qualified Research Institutions” (QRIs) to advise sponsors on first-in-human Phase I clinical trial applications. The commenters also discuss lessons from comparable early-phase trial models in China and Australia.
View Source

Comments on Request for Information, “Commonsense Policy Options to Lower Drug Prices for Patients”

Martin MJ, Anderson KE, Kesselheim AS - Senate Committee on Finance Democrats, 119th Congress

  • Innovation Incentives and Competition
  • Price, Value, and Access
An icon of a bill representing government policy.
The commenters respond to a broad set of policy proposals aimed at improving prescription drug affordability. Among their recommendations, they encourage Congress to let Medicare to negotiate drug prices closer to launch and expand the pool of eligible drugs, address barriers that delay biosimilar uptake, require that patient cost-sharing be based on a drug’s net rather than list price, and establish an independent health technology assessment (HTA) entity to determine whether a drug’s price reflects its clinical benefit.
View Source

Comments on Proposed Rule, “Medicare Drug Price Negotiation Program and Medicare Prescription Drug Benefit Program”

Anderson KE, Cai CL, Hwang TJ, Kesselheim AS, Kim J, Martin MJ, Rome BN - Centers for Medicare and Medicaid Services (CMS)

  • Price, Value, and Access
An icon of a bill representing government policy.
The commenters provide input on several provisions of the proposed rule codifying Medicare drug price negotiation, including CMS’s approach to aggregating reformulated products, assessing bona fide generic and biosimilar competition, and determining the relevant approval date for drugs later deemed biologics. They encourage CMS to be more transparent about how the various exclusions, such as those for orphan drugs and plasma-derived products, affect drug selection, as well as how the agency weighs the evidence considered during negotiations to reach a final maximum fair price.
View Source

Pitfalls of Announcing Regulatory Policy in Medical Journals

Tu SS, Kesselheim AS - BMJ

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Under former Commissioner Marty Makary, the FDA increasingly announced major policy changes through medical journals rather than its normal public rulemaking process. This “policy by publication” approach can confuse patients, clinicians, insurers, and drug companies and limit their opportunity to weigh in before decisions appear final. Medical journals can help explain and debate FDA policy, but they should complement, not replace, transparent policymaking and public participation.
View Source

From Cabozantinib to Zanzalintinib: Obvious Chemical Modifications as a New Frontier in Product Hopping

Strohbehn GW, Tu SS, Wang X, Ratain MJ - Nature Biotechnology

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Exelixis’ development of zanzalintinib, a chemically modified successor to its blockbuster drug cabozantinib (Cabometyx, Cometriq), illustrates how obvious covalent changes to an active ingredient can secure a new composition-of-matter patent and extend market exclusivity ahead of a patent cliff. Lead compound analysis indicates zanzalintinib was legally obvious over cabozantinib, pointing to a need for stronger USPTO-FDA coordination in patent examination to better capture this novel form of product hopping.
View Source

Comments on Section 301 Investigation on Germany’s Persistent Underpayment for Innovative Pharmaceutical Products

Hwang TJ - Office of the US Trade Representative (USTR)

  • Price, Value, and Access
An icon of a bill representing government policy.

Money, Meals, and Marketing in Medicine: A 13‐Year Follow‐Up Survey of Physicians

Mooney H, Austad K, Campbell EG, Avorn J, Lu Z, Kesselheim AS - Clinical Pharmacology & Therapeutics

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among 283 physicians resurveyed 13 years after first participating as medical students and residents, the types of gifts received from pharmaceutical companies remained largely consistent between 2011 and 2024, while there were notable differences in respondents’ use of educational resources to learn about medications. Although ~1 in 4 physicians did not know whether their institution had a policy governing industry interactions, most supported stronger limits on interactions between physicians and the pharmaceutical industry.
View Source

Comments on Reauthorization of the Medical Device User Fee Amendments, FY 2028-2032

Hwang TJ, Bucha S, Kesselheim AS - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
FDA should convert at least one outcome measure for its Total Product Life Cycle Advisory Program (TAP) into a formal, annually reported performance commitment as the program expands across all device areas, and should establish new commitments on the quality of predicate selection and substantial equivalence determinations in 510(k) review. The agency should also coordinate with CMS so that class II devices qualify for expedited coverage pathways such as RAPID only when clearance rested on clinical evidence in populations representative of Medicare beneficiaries, and should require that AI-enabled devices citing only non-AI predicates demonstrate safety and effectiveness through device-specific performance data.
View Source

Clinical Development, Regulatory, and Reimbursement Review Duration of New Drugs in the US and European Countries

Hediger S, Glaus CEG, Dusetzina SB, Rohr UP, Hwang TJ, Vokinger KN - JAMA Health Forum

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among new drugs approved between 2014 and 2024, median time from clinical trial initiation to reimbursement was 9.3 years in the US, 11.1 years in France, 8.9 years in Germany, and 9.8 years in Switzerland, with clinical development accounting for the largest share of total time in all 4 countries. Despite policy efforts to speed drug approvals, total duration changed little over the decade in any country, highlighting the need for further research into policies that can safely accelerate clinical development.
View Source

Brief of Intellectual Property Scholars in xAI v. Bonta

Kesselheim AS, Tu SS - US Court of Appeals for the Ninth Circuit

  • Innovation Incentives and Competition
An icon of a bill representing government policy.
xAI mischaracterizes Ruckelshaus v. Monsanto by treating it as establishing a per se taking whenever a government requires disclosure of trade secret information, as California’s AI training data transparency law does, when in fact Monsanto requires a governmental promise of secrecy, absent from the state’s law, for any such takings claim to succeed. The amici warn that accepting xAI’s broad interpretation would let companies challenge transparency mandates as unconstitutional takings across other domains, chilling state regulation of AI as well as disclosure requirements covering drug prices, hazardous chemical spills, and cosmetics ingredients.
View Source

Comments on the Draft Royal Decree Regulating the Pricing and Reimbursement of Medicines in the Spanish National Health System

Tibau A, Kesselheim AS, Hwang TJ - Ministerio de Sanidad de España

  • Price, Value, and Access
An icon of a bill representing government policy.
The Ministry of Health should adopt an explicit methodology for assessing clinical benefit, specifying appropriate comparators, evidence quality standards, and validated tools such as the European Society for Medical Oncology Magnitude of Clinical Benefit Scale (ESMO-MCBS), and should reconcile the several overlapping benefit definitions used across the decree. Reassessment of reimbursed medicines should be mandatory every three to five years rather than discretionary, and assessment bodies should have access to actual net prices, with limits on confidential discounts that weaken public negotiating power and undermine international reference pricing.
View Source

When Celebrities Prescribe — Regulating Drug Promotion on the Internet

Krüger N, Kong Y, Bachinger M, Kesselheim AS - New England Journal of Medicine

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Patient-targeted promotion of prescription drugs has expanded beyond traditional advertising to the Internet, with celebrities and influencers increasingly endorsing products such as GLP-1s, often evading regulatory scrutiny when promotion comes from social-media figures or telehealth companies rather than manufacturers directly. Stronger guardrails are needed, including updated FDA and FTC guidance on drug risk disclosure in advertising and expanded oversight of drug-class promotion.
View Source

Testimony: Advancing Innovation in Early-Stage Clinical Trials: Policy Options for Reauthorization of the User Fee Agreements

Hwang TJ - 119th Congress, House Committee on Energy and Commerce, Subcommittee on Health

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
Early-stage clinical trial activity, particularly for cancer drugs, is increasingly shifting from the US to China even as the FDA remains the world’s leading regulator for novel drug approvals. To reverse this shift while preserving FDA’s evidentiary standards, recommendations ahead of upcoming user fee agreement reauthorization include raising global clinical trial standards, targeting fee and tax incentives toward small and academic sponsors conducting US trials, expanding transparency around clinical holds, and adding guardrails to FDA’s proposed Expedited IND Pilot Program.
View Source

Savings Under Most-Favored-Nation Pricing for Prescription Drugs in Medicaid

Hwang TJ, Clemans-Cope L, Kesselheim AS - JAMA

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
CMS’ proposed GENEROUS payment model, which would apply most-favored-nation pricing to brand-name drugs in Medicaid, was projected to generate an estimated $8.6 billion in savings across 47 states and the District of Columbia, accounting for nearly 35% of net Medicaid spending after rebates. These savings would be concentrated among newer products and states that currently negotiate smaller supplemental rebates.
View Source

Brief of Public Health and Health Law Scholars In Re: 2025 Subpoena to Children’s National Hospital

Kesselheim AS - US Court of Appeals for the Fourth Circuit

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
The Department of Justice has subpoenaed hospitals providing gender-affirming care to minors on a theory that mischaracterizes the Federal Food, Drug, and Cosmetic Act, treating physicians’ off-label prescribing as a potential basis for civil or criminal liability when Congress, the courts, the FDA, and the Department itself have long understood the Act to regulate manufacturers and distributors rather than individual clinical decisions.The amici, represented by Harvard Law School’s Center for Health Law and Policy Innovation, warn that accepting the Department’s theory would leave no legal protection for off-label prescribing generally and would let federal officials use investigative powers to chill medical practice disfavored by the sitting administration.
View Source

Prevalence and Frequency of Haematological Testing in Patients Initiating Clozapine in the USA

Bykov K, Mahesri M, Huybrechts KF, Moran LV, Hwang CS, Wang J, Lii J, Toyserkani GA, Zhou EH, LaCivita C, Dal Pan GP, Kesselheim AS, Sarpatwari A - BMJ Mental Health

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among more than 54,000 patients initiating clozapine from 2000 to 2022, roughly 30% had no evidence of blood testing in the 60 days before therapy began, and testing during the first 6 months averaged 2.2 tests per 30 days, well below the 4 required under the FDA’s clozapine Risk Evaluation and Mitigation Strategy (REMS). Testing rates were more in line with REMS requirements during months 7 through 24. The FDA eliminated the clozapine REMS in June 2025, but monitoring recommendations remain in the drug’s labeling, so the reasons for less-than-expected early testing warrant further investigation.
View Source

Clinical Outcomes After Antipsychotic Discontinuation in Nursing Home Residents with Dementia: A Nationwide Cohort Study

Yang CT, Wilkins JM, Kesselheim AS, Kim DH, Lin KJ - Alzheimer's Therapy & Research

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a national study of US nursing home residents with dementia who had been taking antipsychotic medications long term, discontinuing these medications was associated with fewer hospitalizations, particularly for pneumonia and urinary tract infections, compared with continuing treatment. The findings support current recommendations to regularly reassess and discontinue long-term antipsychotic use in individuals with dementia when clinically appropriate.
View Source

PORTAL Post | July 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The July 2026 edition of the PORTAL Post monthly newsletter.
View Source

Identifying Diabetic Ketoacidosis Encounters at Diagnosis Among Children with Type 1 Diabetes in Claims Data

McQueen BR, Chen NC, Gutierrez EJ, Anderson KE, Alonso GT - Journal of the Endocrine Society

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among 728 Colorado children newly diagnosed with type 1 diabetes between 2014 and 2019, 56% had diabetic ketoacidosis (DKA), a life-threatening complication of untreated diabetes, at diagnosis, but ICD-based billing code algorithms inconsistently identified these cases in claims: a strict definition requiring both DKA and type 1 diabetes codes missed 37% of true cases, while a broader definition captured 89% but misclassified more children without DKA. These findings suggest claims-based algorithms likely undercount DKA at diagnosis, warranting sensitivity analyses in future research.
View Source

Comments on Legislative Discussion Draft, “Next-Generation US Clinical Development to Accelerate Cures”

Kesselheim AS, Martin MJ, Cliff ERS, Hwang TJ, Tibau A - Office of Representative Jack Auchincloss, 119th Congress

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
Congress should preserve FDA’s authority over first-in-human studies rather than delegating oversight to pre-certified third parties, which would limit the agency’s ability to halt unsafe trials and introduce conflicts of interest where reviewers depend on sponsor funding. Early-phase development could instead be accelerated by standardizing FDA communications from the pre-Investigational New Drug (IND) stage onward, funding additional reviewers, and requiring mutual recognition of institutional review board (IRB) approvals across sites. Requirements that clinical data be generated in the US risk raising development costs and prompting other countries to impose reciprocal local data mandates.
View Source

Comments on the Commissioner’s National Priority Voucher (CNPV) Pilot Program

Hwang TJ - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
These comments, submitted as a follow-up to testimony at FDA’s June 4, 2026 public hearing, recommend that FDA pause the Commissioner’s National Priority Voucher pilot until Congress authorizes it, given that regulatory review accounts for less than a tenth of drug development timelines and that the program risks politicizing approval decisions while imposing an unfunded workload on FDA reviewers. Should the program proceed, vouchers should be limited to generic drugs, and the agency should address reviewers’ reported concerns about the program, require advisory committee review of drugs seeking voucher-based approval, and provide more robust opportunities for patient and public input during the voucher selection process.
View Source

Risk of Bias and Clinical Benefit of Phase III Trials Supporting FDA-Approved Anticancer Medicines, 2018–2025: A Cross-Sectional Analysis

Li G, Pu Y, Chen C, Kesselheim AS, Tibau A - European Journal of Cancer

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among 43 pivotal phase III randomized trials supporting FDA approvals of anticancer drugs, only 30% of trials were at low risk of bias and 33% demonstrated substantial clinical benefit, while just 9% achieved both. FDA regulatory review documents frequently provided methodological information that reduced uncertainty compared with published reports. These findings highlight the importance of integrating trial quality and clinical benefit assessments to strengthen regulatory decision-making, inform clinical practice, and support value-based oncology care.
View Source

Assessing Drug Efficacy After Multiple Negative Trials—Gepirone’s Journey Through the FDA

Turner EH, Powers JH, Ahn-Horst RY, Kesselheim AS - JAMA Psychiatry

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
This case study traces how the antidepressant gepirone ER won FDA approval in 2023 on just 2 positive trials out of 13, after four prior rejections and a negative advisory committee vote. The authors argue this reflects the FDA’s reliance on “trial counting” and statistical over clinical significance, and that the label compounds the problem by omitting the 11 negative trials. FDA should report all efficacy trials and an overall effect size in labeling so clinicians can better assess a drug’s clinical benefit.
View Source

“How Are We Going to Be Able to Pull That Off?”: Staff Perspectives on the Early Implementation of Mobile Medication Units in New York State

Miller M, Song M, Bessler A, Ruelas-Vargas K, Frank D, Harris SH, Gibbons JB, Jordan AE, Krawczyk, Saloner B - Addiction Science & Clinical Practice

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Interviews with 16 staff from four opioid treatment programs that launched mobile methadone units found implementation was slowed by inconsistent DEA guidance, vehicle maintenance and parking requirements, workforce shortages, community opposition, and lower-than-expected patient demand. Persistent leadership, sustained state funding, and strong cross-program partnerships helped get units running, suggesting that the potential of mobile units to expand methadone access depends on these factors.
View Source

Efficacy and Toxicity Associated with Cancer Drug Approvals in Switzerland: International Implications

Tibau A, Kesselheim AS, Hwang TJ - Lancet Regional Health - Europe

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The authors comment on a meta-analysis by Rahimzadeh et al. evaluating the clinical benefit and toxicity of cancer drugs approved in Switzerland. Beyond the Swiss context, they explore the global implications of regulatory approvals based on surrogate endpoints and immature survival data, highlighting challenges for evidence standards, patient access, reimbursement decisions, and value-based cancer care.
View Source

Changes in Medication Use After Medicare Part D Annual Out-of-Pocket Spending Caps

Cai CL, Anderson KE, Kesselheim AS, Rome BN - JAMA Health Forum

  • Price, Value, and Access
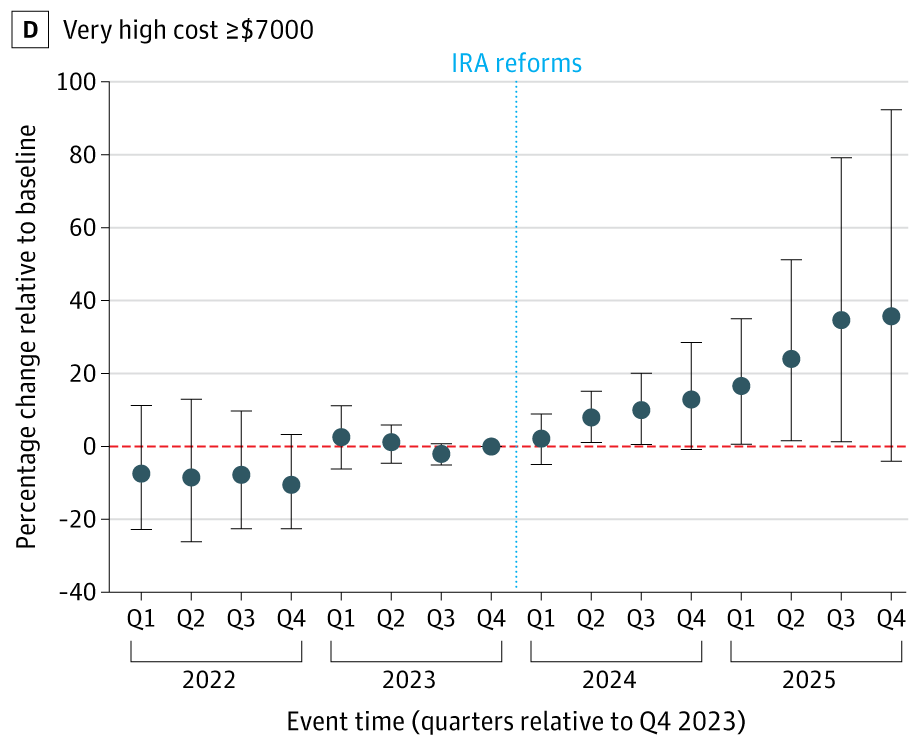
Use of high-cost drugs increased in Medicare after out-of-pocket costs were capped.
After the Inflation Reduction Act capped annual out-of-pocket drug costs for Medicare patients starting in 2024, use of the highest-cost medications (≥$7,000/month) rose 36% within two years compared with privately insured patients. The findings suggest that the out-of-pocket cap improved access to expensive drugs for Medicare patients, although this higher use of costly medications could be associated with substantial increases in Medicare spending.
View Source

Products That Pose Health Risks—Can Litigation Protect Us When Government Fails?

Avorn J - New England Journal of Medicine

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Drawing parallels among recent social media judgments against Meta and YouTube, the Vioxx litigation against Merck, and the 1990s tobacco settlements, the author argues that when Congress and regulators fail to act on clear evidence of harm, lawsuits brought by victims and state attorneys general can force accountability and spur reform. He cautions that juries can sometimes err in assigning blame, but concludes that litigation can serve as a last-resort layer of protection when the usual legislative and regulatory processes fall short.
View Source

High Cost of Cancer Medicines in the United States: Opportunities for Policy Reforms

Tibau A, Vokinger KN, Kesselheim AS, Hwang TJ - JCO Oncology Practice

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Cancer drug prices in the US are substantially higher than in comparable countries, and approximately 1 in 2 patients with cancer experiences financial toxicity. The authors argue that high prices are driven by manufacturers’ ability to set launch prices with limited negotiation, uncertainty surrounding the clinical value of some newly approved drugs, and poor alignment between prices and patient benefit. They suggest that US policymakers draw lessons from international HTA frameworks by linking prices more closely to clinical value and reassessing prices as new evidence emerges.
View Source

Comparing Buprenorphine Treatment Outcomes Among Kentucky Medicaid Patients by Prescriber Specialty and Type

Green VR, Bandara S, Sugarman OK, Gibbons JB, Saloner B, Heidari O - Substance Use & Misuse

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among Kentucky Medicaid patients treated for opioid use disorder, those who received most of their buprenorphine from primary care physicians stayed on treatment longest (covered 69.6% of days vs. 60.1% for specialists and 64.3% for advanced practice providers), while patients of advanced practice providers had the lowest rate of non-fatal overdose. The results suggest that several types of providers can effectively prescribe buprenorphine, supporting efforts to expand who can deliver this treatment.
View Source

Mobile But Still Tied Down: Challenges to Scaling Mobile Methadone Through a Regulatory Thicket

Krawczyk N, Miller M, Frank D, Harris SJ, O'Rourke A, Song M, Ruelas-Vargas K, Gibbons JB, Jordan A, Saloner B - International Journal of Drug Policy

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Using New York’s early rollout as a case study, the authors describe how mobile methadone units remain hamstrung by security rules, high costs, requirements to return daily to a home clinic and stay within state lines, and community opposition. The authors argue that without a broader shift away from “methadone exceptionalism,” mobile units will remain a modest convenience rather than a transformative way to close treatment gaps.
View Source

Using Prescription Drug Data for Timely Assessments of State Insurance Coverage Rates: A Validation Study

Rome BN, McIntyre A, Kim J, Han J, Kesselheim AS, Sommers BD - Health Affairs Scholar

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
State-level prescription fill data tracked closely with Medicaid coverage rates and uninsurance rates from 2013 to 2024. Because these prescription data are available months to years before official coverage figures, they could offer early insight into how new policies limiting Medicaid eligibility affect coverage.
View Source

Comparative Effectiveness Research in Practice: Closing the Gap Between Doctors and Data

Avorn J - TruDataRx Webinar

  • Regulation and Clinical Evidence
Drs. Jerry Avorn and Aaron Kesselheim at the TruDataRx webinar
In a webinar hosted by TruDataRx and PORTAL, Jerry Avorn discusses the long-standing challenge of incorporating comparative effectiveness research (CER) for prescription drugs into clinical practice. He examines why evidence comparing the safety and effectiveness of different treatments has been so hard to get into the hands of clinicians, and strategies to advance evidence-based prescribing and benefit design.
View Source

Use of Leucovorin After the FDA Announcement of Its Use for Autism Spectrum Disorders

Rome BN, Kim J, Figueroa JF, Kesselheim AS - Pediatrics

  • Regulation and Clinical Evidence
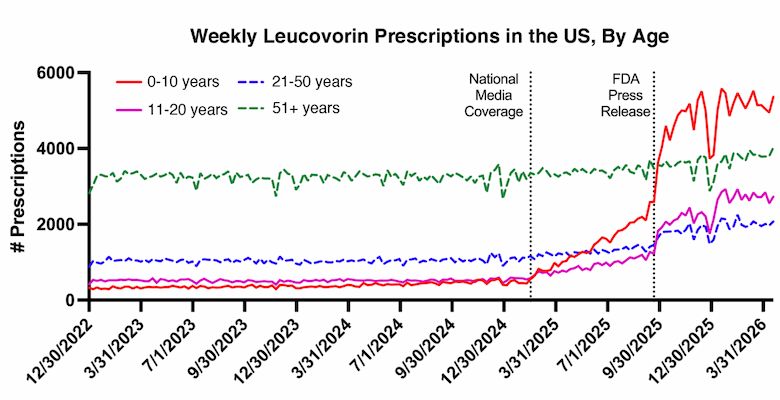
Weekly leucovorin prescriptions in the US, by age (2022-2026)
After national media coverage and a September 2025 White House press conference at which FDA leaders promoted leucovorin as a treatment for autism spectrum disorders, prescriptions among children aged 0–10 rose 14-fold, despite thin evidence of the drug’s effectiveness for treating autism.  This study shows that the FDA’s highly atypical actions in this case had important consequences, including contributing to shortages that may have kept cancer patients from accessing leucovorin for its FDA-approved uses.
View Source

Early Generic Semaglutide in Canada—Implications for US Patients and Policy

Tu SS, Kesselheim AS, Tadrous M, Beall RF - JAMA Internal Medicine

  • Innovation Incentives and Competition
  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Generic semaglutide (Ozempic) is reaching Canada years ahead of the US following the lapse of the single Canadian patent on the product, while 39 patents could block generics in the US until 2041. The authors discuss the implications for US patients, noting that narrow importation pathways are unlikely to meaningfully improve patient access, and that real relief would require patent reform and Congressional authorization to recognize generic drugs approved by trusted regulators like Health Canada.
View Source

When Constitutional Theory Collides With Health Care Accountability—The False Claims Act at a Crossroads

Tu SS, Kesselheim AS - JAMA Health Forum

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
The authors describe a constitutional challenge in Zafirov v. Florida Medical Associates that argues the False Claims Act’s qui tam provisions unlawfully let private whistleblowers exercise executive power, threatening a key tool behind roughly 80% of government fraud recoveries, most of it in health care. Eliminating qui tam suits would gut fraud deterrence, ultimately raising costs and harming patients.
View Source

PORTAL Post | June 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The June 2026 edition of the PORTAL Post monthly newsletter.
View Source

Orphan Designation for Drugs Approved in the United States and European Union: A Comparative Analysis

Costa E, Ross JS, Kesselheim AS - Clinical Pharmacology & Therapeutics

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
The US Orphan Drug Act and EU Orphan Regulation both offer incentives to develop rare disease treatments, but of 344 rare disease drug indications approved from 2011 to 2020, 97.7% received FDA Orphan Drug designation versus only 40.4% from the EMA, with the agencies aligning most on advanced therapies and genetic diseases but diverging on cancer subsets and pediatric indications of common diseases like HIV. These differences reflect the broader US indication-based framework versus the EU’s narrower focus on distinct conditions, suggesting policymakers should target incentives toward truly rare diseases rather than subsets of common conditions like cancer.
View Source

Policy Brief: Eliminating Thickets to Increase Competition (ETHIC) Act

Martin MJ, Tu SS, Kesselheim AS - 119th Congress

  • Innovation Incentives and Competition
An icon of a bill representing government policy.
Brand-name drug manufacturers accumulate thickets of patents on their drugs that they then use to delay generic and biosimilar competition. Studies show many of these patents are obvious variations of earlier patents, granted only after applicants file “terminal disclaimers.” The ETHIC Act allows one patent per group of obvious variation patents to be asserted against generic or biosimilar competitors in litigation, while maintaining brand-name manufacturers’ ability to enforce any patents that fall outside these patent groups. The ETHIC Act substantially reduces the number of patents that could be enforced against generic or biosimilar competitors in litigation, making market entry of generics and biosimilars faster and more efficient, leading to greater health care savings and broader patient access.
View Source

Cost-Effectiveness Thresholds: Overvaluing Innovation, Undervaluing Health

Rand LZG, Paulden M, Raymakers AJN - Health Affairs Forefront

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Standard cost-effectiveness thresholds used in the US and other high-income countries already exceed the marginal cost of a unit of health, building in an “innovation premium” that allows new drugs to be deemed cost-effective even when adopting them produces a net population health loss. Rather than abandoning thresholds, policymakers should fund research to identify the true opportunity-cost threshold, use it as a primary result in analyses, and acknowledge this premium for “newness” as a deliberate policy choice rather than a hidden default.
View Source

What Utah’s Clinical AI Sandbox Reveals About Independent Oversight

Gorijavolu R, Jaiswal N, Kesselheim AS, Sakran JV, Hernandez-Boussard T, Celi LA - Nature Medicine

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Utah became the first state to authorize an AI sandbox for prescription renewals, but a transparency audit of the pilot found that neither the participating company nor the state would release the underlying safety data, performance metrics, or adverse event reports, with operational metrics classified as protected trade secrets. Because a regulatory framework cannot rely on a company as the sole source of safety evidence, the authors propose a Registry of Independent AI Auditors that would mandate external evaluation as a condition of sandbox participation while preserving commercial confidentiality.
View Source

Changes in the Use of Montelukast for Asthma After a US Food and Drug Administration Boxed Warning

Shanmugam H, Kesselheim AS, Liu ITT, Feldman WB, Rome BN - JAMA Network Open

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
After the FDA added a boxed warning to montelukast, a widely used asthma drug, over potential neuropsychiatric adverse effects in March 2020, incident prescriptions fell nearly 30% and prevalent use declined across all age groups, with the steepest drop among children. These findings indicate that boxed warnings can meaningfully shift prescribing even when causal evidence is mixed and should be carefully tailored to the strength of available data.
View Source

Geographic Variation in Pharmacy Competition and Social Vulnerability Proximate to Walgreens

Kissi-Twum K, Anderson KE, Mattingly TJ - Research in Social and Administrative Pharmacy

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
With Walgreens planning to close more than 1,200 stores nationwide, this analysis of 8,743 locations found that 85.3% of counties with a Walgreens had low-competition (i.e., fewer nearby alternative pharmacies per capita than the national average), and 334 counties were both low-competition and highly socially vulnerable (based on the CDC Social Vulnerability Index). Because the closure of a Walgreens in these counties could leave residents with few alternatives and longer travel times to access medications, they should be prioritized for contingency measures like telepharmacy or mail-order delivery. Regulators should also incorporate local competition and vulnerability metrics into pharmacy network adequacy standards.
View Source

Healing Our De-Commissioned FDA

Kesselheim AS, Avorn J - Health Affairs Forefront

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Marty Makary’s tenure as FDA Commissioner undercut the principles that made the agency a leading public health institution—sidelining external peer review, enabling scientifically indefensible decisions, and introducing an opaque super-fast-track voucher program—leaving the FDA weaker and less trusted than at any point in 50 years. The next commissioner should be chosen for scientific competence rather than ideology and return the agency to evidence-based decision making, transparency, and public accountability, particularly ahead of the looming user-fee reauthorization.
View Source

Post-Approval Pediatric Use of Drugs Granted Waivers from Pediatric Testing

Liu ITT, Savage TJ, Tsacogianis TN, Kesselheim AS, Sarpatwari A - Clinical Pharmacology & Therapeutics

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
The Pediatric Research Equity Act requires new drugs to be tested in children before approval but allows waivers, often on the grounds that pediatric studies are “impossible or highly impracticable.” Among 291 drugs granted complete waivers from 2007 to 2022, 51% nonetheless had observable pediatric use within 3 years of approval. This off-label use suggests some waived drugs had sufficient uptake to support pediatric trials, and that routine clinical-use data should be monitored to update labeling and inform safe prescribing.
View Source

Clinical Implementation of Multi-Cancer Early Detection Tests: Can We Find a Path Forward?

Tibau A, Kesselheim AS - Nature Reviews Clinical Oncology

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The authors discuss the growing momentum behind multi-cancer early detection (MCED) blood tests, including the Nancy Gardner Sewell Medicare Multi-Cancer Early Detection Screening Coverage Act, which creates a pathway to Medicare coverage to accelerate access once clinical benefit is confirmed. They argue, however, that MCED tests should be evaluated using the same rigorous standards expected of cancer screening programs, including randomized trials assessing mortality outcomes, before widespread adoption.
View Source

Delisting of Pharmaceutical Patents Challenged by the Federal Trade Commission

Leon J, Tu SS, Kesselheim AS, Feldman WB - JAMA Internal Medicine

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Beginning in 2023, the FTC challenged device-only patents on several drug-device combinations, including inhalers, epinephrine, and GLP-1 products, as being improperly listed in the FDA’s Orange Book. Across the 34 targeted products, companies complied with 90% of delisting requests, shrinking the total listed patents by 80% (from 361 to 72) and reducing the median duration of patent protection from 22.3 to 17.0 years for affected products. By lowering the number of patents generic firms must challenge before approval, these delistings could ease generic entry and improve affordability for several high-cost therapies.
View Source

PORTAL Post | May 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The May 2026 edition of the PORTAL Post monthly newsletter.
View Source

Reforming Payment for Clinician-Administered Drugs — Most-Favored-Nation Pricing in Medicare Part B

Hwang TJ, Clemans-Cope L, Kesselheim AS - New England Journal of Medicine

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The Trump administration’s proposed GLOBE model would align Medicare Part B payments for clinician-administered drugs with international pricing benchmarks, with CMS estimating $11.9 billion in Medicare savings and $6.2 billion in reduced beneficiary cost-sharing over seven years. The model would be strengthened by incorporating clinical benefit into rebate determinations, replacing the lowest-available-list-price benchmark with average international prices to reduce manufacturer gaming, and expanding the program nationwide if evidence of improved health outcomes emerges.
View Source

Op-Ed: Congress Must Repair USPTO’s Inter Partes Review Process

Tu SS, Rai AK, Kesselheim AS - Law360

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Recent administrative changes at the USPTO, including centralized institution authority, unexplained discretionary denials, and non-merits-based decision criteria, have sharply constrained access to inter partes review and are now spreading to ex parte reexamination, leaving fewer viable mechanisms to challenge potentially invalid patents. Congress should enact legislation requiring written explanations for all denials, subjecting those decisions to judicial review under the Administrative Procedure Act’s arbitrary and capricious standard, and reestablishing IPR’s core function of removing erroneously granted patents to protect competition and the public interest.
View Source

Implications of Medicare Negotiation and Most-Favored-Nation Pricing for Cancer Medicine Costs

Hwang TJ, Tibau A, Kesselheim AS, Vokinger KN - JAMA Health Forum

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In this cohort study of brand-name cancer drugs in Medicare Part B and Part D, applying most-favored-nation (MFN) pricing tied to international benchmarks in 2024 could have reduced Medicare drug spending by an incremental 28-41% compared to Medicare negotiation alone. However, the long-term sustainability of MFN savings is uncertain given the potential for manufacturer gaming, and policymakers should explore sharing savings with patients by eliminating out-of-pocket costs for highly effective therapies.
View Source

Deeming Doesn’t Deliver: Reliance on Foreign Regulators Targets the Wrong Stage of Canadian Drug Access

Eisenkraft Klein D, Kesselheim AS - Health Policy

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The authors argue that Health Canada’s proposal to deem certain drug submission requirements met based on foreign regulatory decisions targets the wrong stage of Canada’s drug access pipeline. The primary drivers of delayed access are manufacturers’ late submissions and prolonged public reimbursement processes, not regulatory review times. More impactful reforms would include incentives for earlier manufacturer filings, enforceable timelines for reimbursement negotiations, and a pan-Canadian listing default to meaningfully accelerate patient access to new therapies.
View Source

Prescription Drugs Affected by an Expanded Rare Disease Carve-Out from Medicare Price Negotiation

Rome BN, Mooney H, Kesselheim AS - Journal of General Internal Medicine

  • Innovation Incentives and Competition
  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
The One Big Beautiful Bill Act (OBBBA) expanded exemptions from Medicare drug price negotiation to include drugs approved for multiple rare diseases and delayed negotiation timelines for drugs first approved for a rare disease. The authors identified 22 drugs, collectively accounting for $18 billion in 2023 Medicare spending, that would be exempted or delayed from negotiation under these new provisions. Congress should consider more targeted approaches, such as setting a higher spending eligibility threshold for rare disease drugs, to preserve savings while maintaining protections for rare disease products.
View Source

Comments on Draft Guidance, “Considerations for the Use of the Plausible Mechanism Framework to Develop Individualized Therapies that Target Specific Genetic Conditions with Known Biological Cause”

Tibau A, Martin MJ, Kesselheim AS, Hwang TJ - Food and Drug Administration (FDA)

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
FDA should limit the proposed plausible mechanism framework to ultra-rare diseases so that its flexible evidentiary standards do not extend to conditions for which established approval pathways already exist, and should direct qualifying products to accelerated approval rather than traditional approval. For therapies approved using this framework, FDA should also require robust post-marketing safety follow-up, provide greater transparency on the predictive validity of surrogate endpoints used, and ensure that the drug’s label clearly discloses the limitations of the supporting evidence.
View Source

Using Regression Discontinuity in Time to Strengthen Real-World Evidence: A Case Study in Lung Cancer

Chen NC, Zemplenyi AT, Adamson B, Kaizer AM, O’Bryant CL, McQueen RB, Anderson KE - Medical Decision Making

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Using a real-world cohort of 1,975 patients with advanced non-small-cell lung cancer, the authors applied regression discontinuity in time (RDiT) to estimate the comparative effectiveness of pembrolizumab versus docetaxel while addressing unmeasured confounding from historical controls. RDiT produced survival estimates more closely aligned with long-term clinical trial data than traditional propensity score methods, suggesting it may be a valuable tool for generating credible real-world evidence to inform regulatory, coverage, and drug pricing decisions.
View Source

Closing the Evidence Gap for Drugs in Children — Measures to Strengthen the Pediatric Research Equity Act

Liu ITT, Bourgeois F - New England Journal of Medicine

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The Pediatric Research Equity Act (PREA), the primary US law requiring that new drugs be tested in children, has been undermined by persistent delays in pediatric trial initiation, weak enforcement mechanisms, and statutory gaps that exempt roughly 20% of new drugs and the majority of orphan-designated drugs from pediatric study requirements. The authors recommend that Congress strengthen PREA by requiring pediatric trials to be initiated before adult drug approval, improving enforcement of study deadlines, and expanding the FDA’s authority to require pediatric studies beyond proposed adult indications and for orphan-designated products.
View Source

Anticompetitive Mergers — Pharmaceutical Buyouts as a Strategy for Maintaining Market Dominance

Tu SS, King J - New England Journal of Medicine

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Pharmaceutical “killer acquisitions,” in which incumbent firms buy out smaller competitors to shelve or delay their products, pose a threat to competition and innovation that current antitrust frameworks under the Hart-Scott-Rodino Act are poorly equipped to catch. The authors recommend coordinated legislative and regulatory reforms to better protect competition and patient interests, including lowering notification thresholds for concentrated industries, accounting for intangible assets like patents in merger valuations, and applying heightened scrutiny to acquisitions involving overlapping products.
View Source

Op-Ed: Congress Can Finally Stop Big Pharma’s Patent Abuse

Tu SS - DC Journal

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Branded drug manufacturers have long exploited obviousness-type double patenting to amass dense webs of duplicative patents, forcing generic and biosimilar challengers to litigate each one and effectively blocking competition long after drugs can reasonably be considered innovative. The ETHIC Act would address this abuse by limiting brand-name companies to asserting only one patent per terminal-disclaimer-linked patent group against generic or biosimilar challengers, ensuring patent protection reflects true innovation rather than strategic gamesmanship.
View Source

Skinny Labels at the Supreme Court—Generic Competition, Patent Inducement, and Affordable Medicines

Tu SS, Tessema FA, Kesselheim AS - JAMA

  • Innovation Incentives and Competition
  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The skinny label pathway, which allows generic manufacturers to enter the market by omitting patented indications from their labels, is under threat following Federal Circuit decisions in GlaxoSmithKline v. Teva and Amarin v. Hikma, which expanded induced infringement liability to include truthful, FDA-aligned statements and contributed to a sharp drop in skinny labeled generic entries. With Amarin now before the Supreme Court, the authors recommend ways the Court can clarify the skinny label safe harbor, warning that failure to do so risks undermining a cornerstone of the Hatch-Waxman Act and prolonging brand-name drug monopolies.
View Source

Out-of-Pocket Spending for Insulin by Medicare Beneficiaries After Monthly Caps

Hong D, Cantos K, Morgenstern D, Dasgupta S, Kesselheim AS, Song Z, Tong AY, Chadaram R, Potter D, Patorno E, Avorn J, Rome BN - JAMA Internal Medicine

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In an interrupted time-series analysis of 4.8 million Medicare beneficiaries with type 2 diabetes from 2019-2023, implementation of a $35 monthly insulin out-of-pocket cap was associated with substantial declines in insulin out-of-pocket spending, modest increases in insulin use, and decreases in patient blood glucose levels. These findings suggest that federal cost-sharing caps can meaningfully improve patient access and adherence to essential medicines like insulin for patients with chronic conditions.
View Source

Industry Payments and Prescribing of Brand-Name Multiple Sclerosis Medications in Medicare

Patel AN, Kesselheim AS, Rome BN - Neurology

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a cross-sectional study of clinicians who prescribed two multiple sclerosis drugs to Medicare patients, those who received payments from the brand-name drug manufacturers were more likely to prescribe the brand-name version rather than available generic equivalents. This suggests that these industry payments may be undermining generic competition and leading to higher costs for patients and the health care system.
View Source

PORTAL Post | April 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The April 2026 edition of the PORTAL Post monthly newsletter.
View Source

Global Access to Commercial CAR T Cells: A Cross-Sectional Study of Health Technology Assessment in the G20

Ge AY, Feldman WB, Kaiser MF, Rejeski K, Iacoboni G, Narula G, Chan JY, Dickinson M, Kesselheim AS, Cliff ERS - Blood

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Fewer than half of FDA-approved CAR T-cell therapy indications are reimbursed by health systems in the G20 countries, despite their strong clinical benefits. Many national health technology assessments cited high costs, limited evidence maturity, logistical challenges, and uncertainty about long-term outcomes as barriers to coverage, highlighting the need for new strategies and policy interventions to expand global patient access to CAR T therapies.
View Source

Inflation Reduction Act Changes to Part D Plan Design: Lower Premiums, Higher Deductibles, and Some Smaller Formularies

Anderson DM, McEnany M, Petry SE, Anderson KE - Health Affairs

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Following the redesign of Medicare Part D under the Inflation Reduction Act, actual deductibles were higher than predicted based on 2021-2024 trends for both MA-PD plans ($305 vs. $188) and standalone Part D plans ($491 vs. $401). By contrast, premiums were lower than predicted, and Part D plan formularies shrank for protected classes and lower-cost-sharing tiers with no changes in prior authorization, step therapy, or preferred pharmacy network size. The authors conclude that insurers responded to the increased risk-bearing obligations from the Part D redesign primarily by raising deductibles rather than through utilization management or network restrictions, and they call for continued monitoring as the Premium Stabilization Demonstration expires in 2027.
View Source

National Prescribing Trends of Direct-Acting Antivirals for Hepatitis C

Kishore S, Hayden M, Johnson M, Kesselheim AS, Rome BN - JAMA

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
National prescribing of hepatitis C direct-acting antivirals peaked at 185,677 treatment courses in 2015 but has since fallen to about 69,000 annually, far below the level needed to achieve national elimination targets. Despite shifts toward treatment among Medicaid patients, younger adults, and rural populations, overall treatment volume remains insufficient to reduce national prevalence. These findings highlight the need for expanded screening, rapid treatment models, and policy reforms to accelerate treatment in the US.
View Source

Relevant Industry Payments to 2023–2024 Voting Members of the Advisory Committee on Immunization Practices

Alpern JD, Kesselheim AS - Journal of General Internal Medicine

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among 23 physician members who voted on the ACIP between 2023 and 2024, only 5 (22%) received industry payments relevant to a vote during their tenure, of which 93% were research payments rather than personal compensation. These findings refute claims that the former ACIP was plagued with industry conflicts of interest, and the authors argue that future policy decisions impacting the committee should be data-driven.
View Source

Brand Manufacturer Coupons and Pharmaceutical Product Hopping

Gibbons JB, DiStefano M, Anderson GF, Kesselheim AS, Socal M - JAMA Network Open

  • Innovation Incentives and Competition
  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In an analysis of over 380,000 prescription claims for 47 biologic products, manufacturer coupon use for biologic line extension products increased by 19% relative to comparators as the originator products approached 12 years after market approval when market exclusivity protections began to expire. Among products with older originators, coupons for product hops offset nearly 40% more of patient cost-sharing than comparators, suggesting manufacturers may use coupon programs strategically to facilitate product hopping and dampen biosimilar competition.
View Source

Fluticasone- vs Budesonide-Based Dual Therapy for COPD

Feldman WB, Ambati VL, Suissa S, Kesselheim AS, Avorn J, Schneeweiss S, Wang SV - JAMA Network Open

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a large cohort study of new ICS-LABA users with COPD, the once-daily dry powder inhaler fluticasone furoate-vilanterol was associated with a 9% lower risk of moderate or severe COPD exacerbations compared with budesonide-formoterol and a 6% lower risk compared with fluticasone propionate-salmeterol, with no differences in pneumonia risk. These findings suggest that dry powder fluticasone-containing inhalers offer similar or slightly improved clinical outcomes for patients with COPD over metered-dose formulations, with substantially less greenhouse gas emissions.
View Source

Cost-Related Medication Nonadherence After the Inflation Reduction Act

Marinacci LX, Mein S, Rome BN, Wadhera RK - JAMA Internal Medicine

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
The Inflation Reduction Act’s 2024 prescription changes to Medicare Part D were associated with a 4.9% reduction in cost-related medication nonadherence among Medicare beneficiaries relative to privately insured beneficiaries, with an even larger decline (7.8%) among those with multiple chronic conditions. However, no corresponding improvement was observed in broader measures of health care-related financial strain, suggesting that additional policy interventions may be needed to address patient challenges with health care costs.
View Source

PORTAL Post | March 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The March 2026 edition of the PORTAL Post monthly newsletter.
View Source

Bundling Drugs: The Risks Of Combining Copay Assistance

Daval CJR, Bloomfield D, Rome BN, Kesselheim AS - Health Affairs Forefront

  • Innovation Incentives and Competition
  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Eli Lilly’s program linking copay discounts for tirzepatide (Zepbound) to prescriptions for ixekizumab (Taltz) could constitute anticompetitive behavior that harms competition in unrelated markets without producing meaningful price competition. Th authors call on the FTC to evaluate such arrangements and urge Congress to regulate copay assistance programs in commercial insurance.
View Source

The Case Against Six-Month Limits on Buprenorphine Telehealth Prescribing

Klein DE, Bullen M, Zhu DT, Kesselheim AS - Annals of Internal Medicine

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The Drug Enforcement Agency’s (DEA) new rule requiring in-person visits after six months of telehealth-initiated buprenorphine treatment lacks clinical or public health justification and could disrupt care for patients with opioid use disorder. The authors contend that the rule’s seven exceptions are largely impractical for outpatient addiction settings and urge for the removal of the arbitrary time limit.
View Source

Scope and Characteristics of Patients Filling Medications Through Specialty Pharmacies by Ownership Type

Anderson KE, McEnany M, Mattingly TJ - Health Affairs Scholar

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Using Colorado all-payer claims data, the authors found that while only 0.8% of insured patients filled medications at specialty pharmacies, these users were older, more often female, more socially vulnerable, and had significantly higher prescription use than other patients. Vertically integrated specialty pharmacies accounted for most fills, and their users exhibited higher social vulnerability and more complex medication needs, suggesting that legislation banning PBM or insurer ownership of specialty pharmacies could disproportionately disrupt patient access.
View Source

Research Submission to Inform Medicare Drug Price Negotiation, IPAY 2028

Martin MJ, Hwang TJ, Tibau A, Kesselheim AS - Centers for Medicare and Medicaid Services (CMS)

  • Price, Value, and Access
  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
PORTAL submits summaries of peer-reviewed research to inform CMS’s assessment of 15 drugs selected for Medicare price negotiation in Initial Price Applicability Year (IPAY) 2028, including Anoro Ellipta, Biktarvy, Botox, Cimzia, Cosentyx, Entyvio, Erleada, Kisqali, Lenvima, Orencia, Rexulti, Tradjenta, Trulicity, Verzenio, and Xeljanz.
View Source

List Price Reductions Among Brand-Name ICS-LABA Inhalers in 2024 Were Associated With Increased Generic Uptake

Han J, Wang SV, Kesselheim AS, Avorn J, Feldman WB - Health Affairs

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Following the American Rescue Plan Act’s removal of the Medicaid rebate cap in January 2024, brand-name ICS-LABA manufacturers reduced list prices by 21-50%, and generic ICS-LABA use immediately increased by 23%, driven by gains in commercial plans and Medicare. The authors conclude that list these price reductions likely limited brand-name manufacturers’ ability to offer large rebates to PBMs, disrupting financial incentives that had previously suppressed generic uptake.
View Source

Clinical Benefit and the Trump Administration’s Cancer Medicine Reforms

Hwang TJ, Vokinger KN - Lancet Oncology

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
CMS should adopt validated value frameworks like the ESMO-MCBS in Medicare drug price negotiation to target the deepest discounts at low-benefit drugs, align international reference pricing baskets with comparably large markets to avoid delayed access abroad, and pass savings from these programs on to patients through reduced cost-sharing.
View Source

New Medicare Payment Policy on Drug Shortages

Hwang TJ, Choueiri TK, Vokinger KN - JAMA Health Forum

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
CMS’s new Medicare add-on payment for hospitals to maintain 6-month buffer stocks of essential medicines is an important step but is unlikely to meaningfully reduce drug shortages given its narrow hospital eligibility and the limited reimbursement (about 11% of costs). The authors argue that more durable solutions, such as quality-based purchasing and reform of inflation rebates for generics are needed to stabilize the US drug supply.
View Source

The Growing Success of Medicare Drug-Price Negotiation

Rome BN, Kesselheim AS - New England Journal of Medicine

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The second round of Medicare drug price negotiations achieved average price reductions of 44% across 15 drugs, double the savings of the first round. These added savings may reflect both improvements in CMS’ negotiating strategy as well as the negotiation of more low-rebate drugs, such as cancer therapies, for which the savings potential is greater. Despite legal and political challenges, the authors conclude the program is delivering substantial savings and should be expanded to further improve drug affordability in Medicare.
View Source

Comments on Proposed Rule Implementing the Guarding US Medicare Against Rising Drug Costs (GUARD) Model

Hwang TJ, Venkateswaran S, Cai CL, Krishnan A, Martin MJ, Kesselheim AS - Centers for Medicare and Medicaid Services (CMS)

  • Price, Value, and Access
An icon of a bill representing government policy.
The commenters support GUARD Model’s aim of lowering Medicare Part D prescription drug spending and recommen that CMS narrow the reference country basket, use median pricing for international benchmarks, and aggregate international pricing data across dosage forms and strengths to identify the lowest available price.
View Source

Comments on Proposed Rule Implementing the Global Benchmark for Efficient Drug Pricing (GLOBE) Model

Hwang TJ, Venkateswaran S, Cai CL, Krishnan A, Martin MJ, Kesselheim AS - Centers for Medicare and Medicaid Services (CMS)

  • Price, Value, and Access
An icon of a bill representing government policy.
The commenters support the GLOBE Model’s goal of reducing Medicare Part B drug costs through international reference pricing and recommends that CMS use a narrower basket of economically comparable reference countries and define the benchmark using the median of country-level prices rather than the proposed approach.
View Source

Brief of 76 Scholars of Law, Business, Economics, and Medicine in Hikma v. Amarin (Merits)

Carrier MA, Duan C, Tu SS, Kesselheim AS - US Supreme Court

  • Innovation Incentives and Competition
  • Price, Value, and Access
An icon of a bill representing government policy.
Filed in support of Hikma, the amici outline that patent inducement liability has long required specific, unambiguous, and affirmative conduct, and that the Federal Circuit erred by allowing inducement claims based on speculative inferences from generic drug labels, AB-rating designations, and general marketing statements. Such expansion of patent inducement undermines the “skinny label” pathway for generic drugs, distorts innovation incentives toward low-value method-of-use patents, and threatens patient access to affordable medicines.
View Source

Law, Politics, and Expert Panels at the US Food and Drug Administration

Daval CJ, Kesselheim AS - JAMA Health Forum

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The FDA’s recent shift from formal advisory committees to ad hoc “expert panels” risks undermining the agency’s scientific independence by soliciting advice that appears aligned with predetermined policy positions. The authors argue this approach raises legal concerns under the Federal Advisory Committee Act and reflects a troubling prioritization of political signaling over evidence-based decisionmaking.
View Source

Ensuring Integrity of the Medicaid Drug Rebate Program

Abraham PA, Kannarkat JT, Rome BN, Darrow JJ - Therapeutic Innovation & Regulatory Science

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Although the Medicaid Drug Rebate Program has generated substantial savings, persistent drug misclassification and ambiguous price-reporting rules have led to billions in unpaid rebates. The authors conclude that CMS’s 2024 final rule improves program oversight, but stronger enforcement and auditing practices are needed to safeguard the integrity of the program.
View Source

Risk of Neutropenia-Related Hospitalisation Among Clozapine Initiators

Sarpatwari A, Mahesri M, Lii J, Lee SB, Zakoul H, Toyserkani GA, Zhou EH, LaCivita C, Dal Pan GJ, Bykov K, Moran L, Avorn J, Kesselheim AS, Huybrechts KF - BMJ Mental Health

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Clozapine initiators had a markedly higher relative risk of neutropenia-related hospitalization than olanzapine initiators, especially within the first 6 months after initiation, though absolute risks were very low. The findings help contextualize FDA’s 2025 decision to remove the clozapine risk evaluation and mitigation strategy (REMS) while reinforcing the importance of continued monitoring for neutropenia in patients taking clozapine.
View Source

PORTAL Post | February 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The February 2026 edition of the PORTAL Post monthly newsletter.
View Source

Conflicts of Interest in United States Food and Drug Administration Advisory Committees: A Systematic Literature Review

Gentilini A, Raymakers AJN, Rand LZ - Value in Health

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Across 18 studies, financial conflicts of interest were common among FDA advisory committee participants, affecting 15% to over 70% of meetings for committee members and about one quarter of public speakers. While evidence linking member conflicts to committee voting outcomes was mixed, public speakers with financial conflicts were consistently 3 to 6 times more likely to provide testimony in favor of the approval of the drug under review.
View Source

Priority Without Progress: The FDA’s Neglected Tropical Disease Voucher Program After 18 Years

Goh M, Outterson K, Kesselheim AS - Health Affairs Scholar

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Of the 14 priority review vouchers awarded by the FDA for neglected tropical disease (NTD) products since 2007, most went to existing therapies already widely used outside the US, with FDA approval often occurring years after use in regions in which the NTDs were prevalent. These findings suggest that the NTD voucher program largely rewards regulatory submissions rather than innovation. Policymakers should abandon the voucher or implement reforms that tie voucher eligibility to equitable pricing and demonstrable gains in patient access.
View Source

Physician Awareness of FDA’s Relaxation of REMS-Required Laboratory Testing Requirements and Changes in Prescribing Practices During the COVID-19 Pandemic

Hwang CS, Lu Z, Russo M, Zakoul H, Toyserkani GA, Zhou EH, LaCivita C, Dal Pan GJ, Kesselheim AS, Sarpatwari A - Drug Safety

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
About half of surveyed physicians were aware of the FDA’s temporary policy during the COVID-19 pandemic that allowed clinicians to use medical judgment in place of certain REMS-required laboratory tests, and far fewer physicians reported changing their testing practices in response, often citing the perceived clinical importance of continued monitoring. Targeted, reinforced FDA communication may be needed to ensure clinicians receive and act on temporary policy changes moving forward.
View Source

The 25th Anniversary of a Nearly Unknown Health Policy Turning Point

Avorn J - New England Journal of Medicine

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
A grassroots campaign by clinicians in the late 1990s nearly succeeded in mandating universal health care coverage in Massachusetts, laying the foundation for later reforms like “Romneycare” and the Affordable Care Act. Citizen-driven efforts can spark major policy changes, even with limited resources, offering lessons for today’s ongoing challenges in expanding access to affordable health care.
View Source

Tumultuous Development of Venetoclax in t(11;14) Multiple Myeloma

Kaiser MF, Cliff ERS - Journal of Clinical Oncology

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Venetoclax (Venclexta) demonstrated early, biologically coherent activity in t(11;14) myeloma, but an all‑comer phase 3 strategy produced safety concerns and regulatory freezes that ultimately blocked access even for likely responders. Drug development and regulatory pathways must better accommodate strong biological signals in small subgroups to avoid repeating failures that strand effective therapies.
View Source

Physician Antibiotic Prescribing Preferences in Community Acquired Pneumonia and Complicated Urinary Tract Infections: A National Discrete Choice Experiment

Hong D, Kesselheim AS, Metlay JP, Powers JH, Morlock R, Feldman WB - Open Forum Infectious Diseases

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a discrete choice experiment, physicians were found to prioritize rapid symptom improvement and dosing convenience over side-effect risks and future antibiotic resistance when selecting antibiotics to treat community-acquired pneumonia and complicated urinary tract infections, with variation by specialty and practice setting. These prescribing preferences can inform antibiotic stewardship efforts and guide development of antibiotic trials with clinically meaningful endpoints.
View Source

Physician Perspectives on Real-World Evidence for Prescribing to Older Patients

Rand LZG, Wang J, Woloshin S, Wang SV, Darrow JJ, Kesselheim AS - Journal of Pharmacy Practice

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Interviewed physicians saw real-world evidence (RWE) as valuable for filling evidence gaps when prescribing medications to older adults, but expressed concerns about data quality, confounding, and interpretation of such information, emphasizing reliance on trusted sources such as professional guidelines. Closer collaboration between RWE researchers and guideline developers is necessary to ensure actionable, clinically meaningful dissemination of RWE.
View Source

Out-Of-Pocket Spending for Biologic Drugs After Biosimilar Competition for Medicare Patients

Riegler JS, Kesselheim AS, Rome BN - JAMA Network Open

  • Innovation Incentives and Competition
  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among nearly 275,000 Medicare Advantage patients who used one of seven clinician‑administered biologics, average annual out-of-pocket spending fell by about $94 within four years of biosimilar competition, with savings concentrated among patients with coinsurance or deductibles. These findings contrast reports of inconsistent out-of-pocket savings for patients with private insurance, suggesting that Medicare’s reimbursement for biologics based on average sales prices allows biosimilar competition to translate more directly into patient savings.
View Source

PORTAL Post | January 2026

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The January 2026 edition of the PORTAL Post monthly newsletter.
View Source

Generic Liraglutide—Overlooked but Not Forgotten

Gondi S, Kesselheim AS, Rome BN - New England Journal of Medicine

  • Innovation Incentives and Competition
  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The arrival of generic liraglutide offers a lower-cost option for treating diabetes and obesity, which could help expand access and reduce financial strain on health systems grappling with skyrocketing GLP-1 drug spending. Insurers, clinicians, and patients should consider generic liraglutide, noting its proven effectiveness and safety, even though newer GLP-1 medications are more convenient and effective.
View Source

The Curious Constraints on Clofazimine

Goh M, Eisenkraft Klein D, Kesselheim AS - Journal of Antimicrobial Chemotherapy

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Despite decades of safe use, access to clofazimine, a WHO-recommended treatment for leprosy and emerging therapy for drug-resistant tuberculos,remains limited in the US and other high income countries due to reliance on a single manufacturer and complex expanded access pathways. Streamlining regulatory and procurement processes, as well as expanded public manufacturing capcity, can help ensure equitable supply of this essential medicine.
View Source

Combination-Only Approvals as a Barrier to Affordable HIV Care

Tu SS, Bonis T, Sinha MS, Slade DH - JAMA

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
“Combination-only” drug approvals, in which new HIV medications are approved only as part of multi-drug combinations and not as standalone products, are keeping HIV treatment costs high by blocking generic competition and preventing cost-saving regimen changes. To expand affordable access to HIV care, the FDA should require that new drugs used in combinations also be approved as monotherapies
View Source

Tertiary Patents on Drugs Approved By the FDA

Teng TW, Tu SS, Mooney H, Bendicksen L, Gabriele SME, Wouters OJ, Feldman WB - JAMA Health Forum

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a review of over 300 drug-device combinations approved by the FDA from 1986 to 2023, tertiary patents on the delivery device made up more than half of the patents listed for these products.These tertiary patents extended market exclusivity periods by a median of 7.5 years, despite nearly 60% of these patents not mentioning the drug’s active ingredient. Policymakers and regulators should improve oversight of tertiary patents to mitigate such improper Orange Book listings and to ensure timely generic competition.
View Source

Changes in Medication Use During Medicaid Continuous Enrollment and Unwinding

Rome BN, Han J, McIntyre A, Kesselheim AS, Sommers BD - JAMA Health Forum

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Expanded Medicaid enrollment during the COVID-19 continuous coverage period and the subsequent unwinding were associated with corresponding changes in use of prescription medications for chronic diseases, suggesting that these Medicaid policies affected patients’ access to necessary health care. States that implemented protective policies during unwinding experienced smaller decreases in medication use, highlighting the value of efforts to maintain patient access to medications during coverage transitions.
View Source

Using Prescription Medication Utilization Trends to Evaluate Health System Resilience and Inform Future Emergency Preparedness

Dardouri M, Wright G, Saseen JJ, Nair KV, Anderson KE - Journal of Managed Care & Specialty Pharmacy

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In an analysis of prescription medication trends in Colorado during the COVID-19 pandemic, the authors found an immediate drop of 3.3 prescription fills per 100 insured adults, with retail pharmacy prescriptions rebounding over time due to telehealth and mail-order options while physician-administered therapies saw sustained decreases. These findings highlight importance of maintaining telehealth flexibilities and ensuring safe access to in-person treatments to build a more resilient health system for future public health emergencies.
View Source

Stigma, Scarcity and the Price of Legitimacy: Chronic Pain Advocacy and the Politics of Pharmaceutical Partnerships in Canada

Eisenkraft Klein D, Hawkins B, Grundy Q, Schwartz R - Sociology of Health & Illness

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Drawing on interviews with 22 Canadian chronic pain advocates, this study shows pharmaceutical funding was widely viewed as a pragmatic response to stigma, weak public funding, and institutional neglect rather than as simple ethical capture. The authors conclude that these structural constraints entrenched pharmaceuticalized approaches to pain advocacy, even as industry ties later became a source of reputational liability.
View Source

Characteristics of Speakers at US FDA Advisory Committee Meetings on Drug Approval

Rand LZG, Mooney H, Hong D, Eisenkraft Klein D, Kesselheim AS, Rome BN - JAMA Internal Medicine

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
During the 161 FDA advisory committee meetings held from 2015 to 2023, patients and family members made up nearly half of all speakers during public comment periods. 82% of speakers supported drug approval, and speakers reporting conflicts of interest (COI) were 11% more likely to favor approval. These findings highlight the need for COI disclosure and broader stakeholder input at these committee meetings.
View Source

The Pharmaceutical Industry’s Quiet Win in the One Big Beautiful Bill Act

Bucha S, Martin MJ, Feldman WB - Annals of Internal Medicine

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The One Big Beautiful Bill Act benefits the pharmaceutical industry by limiting Medicare’s ability to negotiate drug prices, expanding tax breaks, and shrinking Medicaid coverage. These policy changes are expected to raise health care costs, reduce patient access, and weaken recent drug pricing reforms, prioritizing industry profits over public health and affordability.
View Source

Estimating Racial and Ethnic Disparities in Substance Use Disorder Treatment and Harm Reduction Services: Findings From a Survey of People Who Use Drugs

Gibbons JB, Bandara S, Cook BL, Byrne L, Sugarman OK, Kerins L, Pugh T, Hulsey EG, Heller D, Minna S, Saloner B - Health Services Research

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a survey of 1,651 people who use drugs, Black, Hispanic, and American Indian/Alaska Native respondents reported substantially lower use of harm reduction and substance use disorder (SUD) treatment services than White respondents. The authors conclude that conventional adjustment methods in such studies can mask true inequities and recommend Institute of Medicine-aligned approaches to more accurately measure and address health disparities.
View Source

Patient Perceptions of and Experiences with Risk Evaluation and Mitigation Strategies

Sarpatwari A, Lee SB, Zakoul H, Tekle W, Freedman A, Belitkar S, Toyserkani GA, LaCivita C, Zhou EH, Oswell KH, Dal Pan GJ, Kesselheim AS - Clinical Pharmacology & Therapeutics

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In interviews with patients and caregivers using seven drugs subject to FDA risk evaluation and mitigation strategy (REMS) programs, participants were found to be generally knowledgeable about REMS-related drug risks, but some encountered challenges finding prescribers, navigating testing requirements, and managing the administrative burdens of these programs. REMS programs are effective in educating patients about drug risks, but better integration of REMS into clinical workflows can improve medication access and adherence.
View Source

Outcomes of Nononcology Accelerated Approvals (Reply)

Liu ITT, Kesselheim AS, Cliff ERS - JAMA

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
Surrogate measures used for accelerated approval are, by definition, not fully validated and may lack strong evidence linking them to clinical benefit. The authors highlight recent cases where reliance on such surrogates led to regulatory withdrawals or ongoing uncertainty, and emphasize that while accelerated approval can speed access to new treatments, it also requires careful follow-up and realistic communication about risks.
View Source

Serial Patent Litigation: an Emerging Strategy to Delay Entry of Generic Competition

Bonis T, Kesselheim AS, Tu SS - Health Affairs Scholar

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Brand-name drug manufacturers are increasingly filing repeated, nearly identical lawsuits, known as “serial patent litigation,” to delay the entry of generic competitors and keep drug prices high. This strategy raises costs for generic manufacturers, discourages competition, and ultimately limits patient access to affordable medicines, highlighting the need for legal reforms to protect timely generic entry.
View Source

PORTAL Post | December 2025

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The December 2025 edition of the PORTAL Post monthly newsletter.
View Source

The Strength and Importance of Government-Funded Patents for Approved Drugs (Reply)

Gabriele SME, Martin MJ, Kesselheim AS, Tu SS - Nature Biotechnology

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
In response to a letter about their original analysis, the authors clarify that the Bayh–Dole Act does allow the government to exercise march-in rights when patented, government-funded drugs are not made available on reasonable terms, including cases of excessive pricing. TApplying these rights aligns with Congress’s original intent to ensure publicly funded medicines serve the public interest.
View Source

Discovering a Transformative Cancer Drug: The Case of Ibrutinib

Bendicksen L, King L, Cliff ERS, Kesselheim AS - Drug Discovery Today

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Ibrutinib, originally developed as a tool compound for autoimmune research, was repurposed into a breakthrough cancer treatment. This analysis documents how despite relatively low development costs, ibrutinib’s success was shaped by flexible regulatory approaches, public funding, and the willingness to redefine clinical trial criteria, ultimately leading to over $50 billion in sales and transforming treatment for B-cell cancers while raising affordability and access concerns.
View Source

Constructing Opioid Legitimacy: The Canadian Pain Task Force’s Framing of the Overdose Crisis

Eisenkraft Klein D, Grundy Q, Hawkins B, Schwartz R - Journal of Law, Medicine & Ethics

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Analysis of Canadian Pain Task Force reports, consultations, and interviews shows the overdose crisis was primarily framed as a problem of illicit supply and stigma rather than prescription opioid use. This framing shaped access‑oriented policy recommendations and risks sidelining prescription‑related harms in opioid policymaking.
View Source

Prescription Drugs Subject to a Risk Evaluation and Mitigation Strategy: Patient Perspectives on Risk Communication and the Value of Educational Materials

Chimonas S, Cosenza C, Kesselheim AS, Toyserkani GA, Oswell KH, LaCivita C, Dal Pan GJ, Sarpatwari A - Drug Safety

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In a survey of patients and caregivers with experience navigating FDA risk evaluation and mitigation strategy (REMS) programs, most respondents reported feeling well-informed about the safety risks of their medications, yet their understanding of REMS requirements the value of REMS educational materials varied. These findings highlight the need for clearer, more tailored educational resources and greater provider involvement to improve patient knowledge and adherence to REMS programs.
View Source

Op-Ed: The Trump Administration Is Turning Drug Review Into Make-A-Deal

Carpenter D, Hwang TJ, Kesselheim AS - STAT

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The FDA’s new National Priority Voucher program replaces science-based drug review with deal-making and political bargaining. Vouchers are awarded based on vague “national health priorities” and private negotiations, rather than clear, evidence-based criteria. This approach risks corruption, undermines transparency, and could harm public trust in the FDA.
View Source

US Spending on High-Revenue Rare Disease Drugs in 2022

Mooney H, Kesselheim AS, Rome BN - American Journal of Managed Care

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Nearly one in five of the top 100 highest-revenue prescription drugs in the US were approved only for rare diseases, with spending on these 19 rare disease drugs totaling $45.1 billion, or 7.5% of US prescription drug spending. Excluding rare disease drugs from federal and state drug price policies limits potential savings and patient impact of efforts improve prescription drug affordability.
View Source

Mapping Intellectual Property Abuses in the Pharmaceutical Field

Tu SS, Rutschman AS - JAMA Health Forum

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
This viewpoint provides an overview of how brand-name pharmaceutical manufacturers exploit patents, trade secrets, copyrights, and trademarks to block competition and keep drug prices high, often at the expense of patient access and public health. Stronger patent examination and other legal remedies can curb these intellectual property abuses.
View Source

Enhancing Formulary Accessibility: a Step Toward Better Care

Agbafe VC, Kesselheim AS, Barbieri JS - Journal of General Internal Medicine

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
Making drug formularies more accessible via federal legislation to mandate formulary transparency and integretaton with electronic health records would help clinicians align prescriptions with coverage, reduce administrative burdens, and improve patient adherence.
View Source

Inhaler-Related Greenhouse Gas Emissions in the US: A Serial Cross-Sectional Analysis

Feldman WB, Han J, Raymakers AJN, Furie GL, Chesebro BB - JAMA

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Between 2014 and 2024, the greenhouse gas emissions of asthma and COPD metered-dose inhalers in the US accounted for 98% of the estimated 24.9 million metric tons of CO₂-equivalent emissions during this period, equivalent to 530,000 gas-powered cars on the road each year. Policymakers and regulators should incentivize a shift toward dry powder and soft mist inhalers while facilitating market entry of affordable low-emission metered-dose products.
View Source

Optimizing Oncology Drug Development: Systematic Review of 22 Years of Myeloma Randomized Controlled Trials

Mainou M, Alsadhan M, Tsapa K, Visram A, Mian H, Popat R, Mai EK, Chakraborty R, Al Hadidi S, Mohan M, Szabo A, Van Oekelen O, Cliff ERS, Mohyuddin GR - Journal of the National Cancer Institute

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Across 123 randomized myeloma trials, studies were far less likely to succeed when overall survival was the primary endpoint and when enrolled populations were older. Endpoint selection and trial population design strongly influence apparent trial success and should be explicitly weighed by sponsors and regulators.
View Source

Patient and Population Impacts of Multigene Panel and Pembrolizumab Coverage in Metastatic Melanoma

Weymann D, Krebs E, Pollard S, McPhail M, Bosdet I, Yip S, Weppler AM, Karsan A, Anderson H, Bubela T, Law MR, Kesselheim AS, Regier DA - Journal of the National Cancer Institute

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Expanding coverage for multi-gene panel testing and pembrolizumab in metastatic melanoma patients in British Columbia led to a 111-day increase in two-year patient survival and a mean per-patient cost increase of $53,963. However, these individual gains did not translate into improved population-level mortality, while overall healthcare system costs rose significantly.
View Source

Pricing Trends and Overlapping Indications of Checkpoint Inhibitors for Cancer Treatment

Paul JM, Mitchell AP, Kesselheim AS, Rome BN - JCO Oncology Practice

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Despite the introduction of 11 FDA-approved checkpoint inhibitors for the treatment of cancer between 2015 and 2024, prices for this drug class decreased only slightly, in part because nearly half of approved indications were unique to a single drug, limiting direct competition. Expanding price negotiations and incentivizing comparative effectiveness research could help address persistent high prices for these therapies.
View Source

Therapeutic Value and Regulatory Characteristics of Breakthrough Therapy Drugs in the USA and China (2021-2023): A Retrospective Cohort Study

Mao X, Yin H, Bai X, Kesselheim AS, Li G - Drug Discovery Today

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In this comparison of drugs granted breakthrough therapy designation (BTD) by the US FDA and China’s NMPA, BTD drugs were found in both markets to more often receive accelerated or conditional approval based on limited evidence. Many of these products were also classified as offering only minor or insufficient clinical benefit at market entry. Regulators in both countries should grant BTD more cautiously and emphasize robust, evidence-based evaluation of therapeutic value to ensure this expedited pathway delivers meaningful clinical benefits.
View Source

Real-World Evidence in Drug Approvals at the European Medicines Agency

Bachinger M, Jankowski MA, Kesselheim AS, Krüger N - JAMA Network Open

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Real-world evidence (RWE) was included in fewer than 10% of European Medicines Agency (EMA) drug approval documents from 2020 to 2023, with inconsistent reporting in how RWE was defined and presented. in drug approval decisions from 2020 to 2023. Standardized assessment tools are needed to better incorporate RWE in regulatory decision-making.
View Source

PORTAL Post | November 2025

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The November 2025 edition of the PORTAL Post monthly newsletter.
View Source

Recent Changes in Discretionary Denials of Drug Patent Challenges

Tu SS, Rai AK, Kesselheim AS - Health Affairs Scholar

  • Innovation Incentives and Competition
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
USPTO policy changes that sharply limit administrative patent challenges for drug patents, such as discretionary denials based on “settled expectations,” make it harder to challenge weak patents, potentially delaying generic and biosimilar competition. Congress should clarify and restrict discretionary denials to preserve effective patent oversight and timely access to affordable medicines.
View Source

US Government Spending on New Drugs with Incomplete and Postponed Mandatory Pediatric Trials

Liu ITT, Kesselheim AS - JAMA Pediatrics

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among new drugs approved between 2015 and 2022 that were required to conduct pediatric studies under the Pediatric Research Equity Act (PREA), 38% had their pediatric trials delayed by more than a year, with the US government spending $27 billion on these products through Medicare and Medicaid in the interim. Current enforcement mechanisms to improve compliance with PREA requirements are weak and stricter financial penalties should be used to encourage timely completion of studies.
View Source

Halting Hyaluronidase Hopping to Maintain the Integrity of Medicare Drug Price Negotiation

Kim J, Kesselheim AS, Rome BN - Journal of Managed Care & Specialty Pharmacy

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
A loophole in Medicare drug price negotiation may enable manufacturers of certain intravenously infused biologic drugs to delay negotiation eligibility by launching subcutaneous versions of their products that contain hyaluronidase. CMS should prevent these reformulated versions from delaying price negotiation by bundling reformulated products with their originals to ensure the price negotiation is meeting its intended policy goals.
View Source

Glucagon-Like Peptide-1 Receptor Agonists and Pay-Per-Click Direct-To-Consumer Advertising

Eisenkraft Klein D, Zenone M, Kesselheim AS - JAMA Network Open

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Over two years, $7.5 million was spent on pay-per-click (PPC) direct-to-consumer online advertising to promote semaglutide (Ozempic) in the US, with substantial spending targeting weight-loss keywords and competitor drug names, even though Ozempic is not FDA-approved for weight loss. Given that PPC advertising can influence consumer behavior, the FDA should issue guidelines on appropriate use of this advertising strategy or review PPC content to prevent misleading drug promotion.
View Source

Flaws in the FDA’s New Priority Voucher Program

Carpenter D, Hwang TJ, Kesselheim AS - New England Journal of Medicine

  • Innovation Incentives and Competition
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
The FDA’s new Commissioner’s National Priority Voucher (CNPV) program is flawed, with broad and opaque eligibility criteria that risk politicizing drug approvals and undermining public trust. The program may have little impact on overall drug development timelines, while imposing burdens on agency staff and opening the door to conflicts of interest. The FDA should implement strong safeguards on the CNPV program to ensure transparency, fairness, and regulatory integrity.
View Source

Biosimilar Interchangeability and Substitution in the US: What Comes Next?

Rome BN, Bhaskar A, Kesselheim AS - American Journal of Managed Care

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
FDA regulatory changes that allow more biosimilars to be deemed interchangeable with their reference product are important steps to improve access to biosimilars. However, other policy changes are needed to boost biosimilar competition in the US, including adjusting state laws to more easily permit automatic pharmacist substitution of biosimilars, reforms to pharmacy benefit manager practices, and better clinician and patient education.
View Source

Testimony: Public Funding of R&D and Fair Drug Prices Are Essential to Support Innovation in Biotechnology

Kesselheim AS - 119th Congress, Senate Committee on Health, Education, Labor, and Pensions

  • Innovation Incentives and Competition
  • Price, Value, and Access
An icon of a bill representing government policy.
Kesselheim details how NIH funding has underpinned virtually all major biotechnology innovations and warns that the Trump administration’s proposed 40% NIH budget cut threatens future innovation. He also calls on Congress to eliminate the 4-year “biologic bonus” delay in Medicare drug price negotiation, reverse the expansion of the rare disease carve-out, and take action to address patent thickets to ensure that patients can access breakthrough innovations at fair prices. Watch his testimony.
View Source

Testimony: Reforming the 340B Drug Pricing Program and Ensuring Access to Affordable Medications

Feldman WB - 119th Congress, Senate Committee on Health, Education, Labor, and Pensions

  • Price, Value, and Access
An icon of a bill representing government policy.
Feldman expresses support for reforming the 340B program—which has grown to over $65 billion in annual drug purchases—through improved transparency, stronger HRSA oversight, limits on child sites and contract pharmacies, clearer community benefit standards, and other measures. However, he emphasizes that 340B reform alone will not lower US drug prices and should be paired with other reforms, including protecting and expanding Medicare drug price negotiation, combating patent thickets, and preserving Medicaid and ACA coverage for vulnerable patients. Watch his testimony.
View Source

Op-Ed: Corporate Support Cannot Make Up for Threats to the NIH Budget

Avorn J - STAT

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Phamaceutical industry funding cannot substitute for robust public investment in biomedical research, especially from the NIH. Industry support is often limited to product-driven, patentable research and can restrict open scientific communication, whereas publicly funded research enables broad dissemination of basic scientific research.
View Source

Role of Health Workers and Representative Health Worker Organisations in LMIC Pharmaceutical Policy: A Scoping Review Protocol

Eisenkraft Klein D, Noor MN, Eiwanger L, Linton J, Ellis U, Sriram V - BMJ Open

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
This scoping review protocol outlines a systematic assessment of how health workers and their organizations have shaped pharmaceutical policy in low- and middle-income countries (LMICs).
View Source

Revenue Differences Between Top-Selling Small-Molecule Drugs and Biologics in Medicare

Vogel M, Feldman WB, Cowan Z, Rome BN, Chandra A, Kesselheim AS, Wouters OJ - JAMA Health Forum

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among the top-selling small-molecule drugs and biologics eligible for Medicare drug price negotiation from 2012 to 2022, biologics generated substantially higher cumulative revenues than small-molecule drugs, totaling $4.9 billion more over 9 years and $7.9 billion more over 13 years. These findings suggest the longer exemption period for biologics from price negotiation is unecessary.
View Source

Pharmaceutical Access in Brazil: Challenges and Opportunities

Ruas CM, Portela R, De Assis Acurcio F, Alvares-Teodoro J, Guerra Júnior AA, Kesselheim AS - Globalization and Health

  • Innovation Incentives and Competition
  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In this review of pharmaceutical access in Brazil, the authors note that the Brazilian pharmaceutical market is highly concentrated, with low investment in R&D and heavy reliance on imported active ingredients. High drug prices and drug shortages also contribute to inequities in patient access. Prioritizing R&D investment, reducing dependency on international markets, and other reforms to drug pricing and patent standards can help alleviate these access challenges.
View Source

Trends in Medicare Spending on Drugs for Pulmonary Arterial Hypertension, 2012-2022

Shih JA, Lee CC, Feldman WB - Chest

  • Innovation Incentives and Competition
  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Annual estimated net Medicare spending on drugs to treat pulmonary arterial hypertension (PAH) more than doubled from $1.2 billion in 2012 to $2.8 billion in 2022, driven both by increased use and costs of the medications. By 2022, despite more generic availability, brand-name drugs still accounted for nearly 9 in every 10 dollars spent in Medicare on PAH medications.
View Source

Regulatory and Clinical Outcomes of Nononcology Accelerated Approvals

Liu ITT, Reynolds G, Kesselheim AS, Cliff ERS - JAMA

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In an analysis of 50 non-oncology drugs granted FDA accelerated approval from 2013 to 2024, 38% were converted to full approval at a median 3 years later, but over half of these conversions relied on surrogate endpoints rather than direct clinical outcomes. The study raises concerns about the clinical utility of some accelerated approvals and calls for more robust confirmatory trials to ensure patient benefit.
View Source

Brief of Professors of Law, Medicine, and Public Health in Vanda v. United States

Feldman WB, Kesselheim AS, Tu SS - US Court of Appeals for the Federal Circuit

  • Regulation and Clinical Evidence
An icon of a bill representing government policy.
Vanda mischaracterizes Ruckelshaus v. Monsanto by treating it as establishing a per se taking whenever FDA uses or discloses trade secret information, when in fact Monsanto requires a statutory promise of secrecy, absent from the Food, Drug, & Cosmetic Act, for any such takings claim to succeed. The amici warn that accepting Vanda’s broad interpretation would obstruct generic drug competition under Hatch-Waxman and chill FDA’s ability to communicate essential public health information such as adverse event data, manufacturing inspection reports, clinical trial protocols, and drug shortage information.
View Source

PORTAL Post | October 2025

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The October 2025 edition of the PORTAL Post monthly newsletter.
View Source

Isotretinoin Risk Evaluation and Mitigation Strategy and Pregnancy Incidence

Zhu Y, Anand P, Sarpatwari A, Hernández-Díaz S, Bykov K, Kesselheim AS, Avorn J, Vine SM, Adomi M, DiCesare EC, Mahesri M, Zakoul H, Mogun H, Toyserkani GA, LaCivita C, Zhou EH, Dal Pan GJ, Huybrechts KF - JAMA Internal Medicine

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Initiation of isotretinoin under the iPLEDGE risk evaluation and mitigation strategy (REMS) program was associated with a 70%–80% lower pregnancy incidence than topical retinoids across publicly and commercially insured patients, though differences persisted by insurance type and race/ethnicity. Despite these reductions, fetal exposre to isotretinoin still occurred, highlighting the need for strategies to improve adherence to REMS requirements.
View Source

Changes in Medicare Part D Plan Designs After the Inflation Reduction Act

Cai CL, Bhaskar A, Kesselheim AS, Rome BN - JAMA Internal Medicine

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
After the Inflation Reduction Act (IRA), Medicare Part D plans increased deductibles and relied more heavily on coinsurance for brand-name drugs. For the most common medications, average monthly out-of-pocket costs in Medicare Advantage plans ranged from $46 to $55 between 2019 and 2024 and then increased to $73 in 2025. In standalone plans, mean monthly costs increased from $62 to $108 from 2019 to 2025. While the IRA capped annual out-of-pocket spending at $2,000, these plan design changes may result in higher costs for beneficiaries who do not reach the cap, suggesting a need for further policy action.
View Source

Assessing Outcomes Emerging After Conversion to Regular Approval for Cancer Drug Indications Granted Accelerated Approval, 1992-2021

Tibau Martorell A, Romano A, Liu ITT, Han J, Cliff ERS, Kesselheim AS - Journal of the National Cancer Institute

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among all cancer drug indications granted accelerated approval by the FDA between 1992 and 2021 that were later converted to full approval, only 32% of confirmatory trials used to support full approval showed overall survival benefit and fewer than half (47%) met the ESMO-MCBS threshold for substantial benefit. These findings highlight the need for stronger approval standards for cancer therapies granted accelerated approval and the value of scales like ESMO-MCBS better guide treatment value for patients and clinicians.
View Source

Whose Burden, Whose Benefit? Revisiting Ethical Trade-Offs in the WHO Guidelines on Scaling Up Mass Azithromycin Administration

Goh M, Viens AM, Karim SA, Kesselheim AS, Outterson K - PLOS Medicine

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
The authors critique the World Health Organization’s (WHO) cautious approach to mass azithromycin administration (MDAA) to reduce childhood mortality in high-burden, low-resource settings due to concerns about antimicrobial resistance (AMR). This approach insufficiently addresses justice and equity considerations, and revised WHO guidelines should place greater emphasis on these ethical considerations, expanding eligibility for MDAA based on context-specific criteria and community input.
View Source

Prices and Spending for Phosphodiesterase 4 Inhibitors in Pulmonary and Dermatologic Disease

Perry NJ, Barbieri JS, Rome BN - JAMA Dermatology

  • Innovation Incentives and Competition
  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
In this analysis of US spending on two phosphodiesterase 4 inhibitors, roflumilast and apremilast, the authors found that apremilast was priced 10-times higher than roflumilast, and this gap widened after roflumilast faced generic competition starting in 2022. From 2014 to 2024, apremilast spending totaled $16 billion, which could have been reduced by 84% ($13.5 billion) had roflumilast been substituted. These findings raise concerns about incentives for companies to develop new higher-cost medications rather than repurposing existing ones for new indications.
View Source

Brief of Economists and Scholars of Health Policy in National Infusion Center Association v. Kennedy (5th Circuit)

Frank RG, Scott Morton FM, Kesselheim AS, Anderson GF, Conti RM, Cutler DM, Hoadley J - US Court of Appeals for the Fifth Circuit

  • Price, Value, and Access
An icon of a bill representing government policy.
The amici express support for the Medicare drug price negotiation program and rebut assertions that the program will harm biopharmaceutical innovation. They argue that patents, exclusivity periods, and insurance coverage distort the drug market far from free-market conditions, that continued strong R&D investment and clinical trial activity since the Act’s passage undermine industry claims of innovation harm, and that the program’s structure mirrors fair negotiation processes long used by other federal purchasers.
View Source

FDA Regulatory Pathways for Expedited Drug Development and Approval

Kesselheim AS - Clinical Advances in Hematology & Oncology

  • Regulation and Clinical Evidence
Talk bubble graphics representing commentary and opinion.
While expedited FDA approval pathways can speed patient access to promising new cancer therapies, they also increase the risk of approving drugs with uncertain benefits or safety issues. To mitigate these risks, FDA should provide clearer communication about the nature of expedited approvals, rapidly update drug labels when new evidence emerges, and take action to ensure sponsors complete confirmatory trials in a timely manner.
View Source

Modeling the Budgetary Impacts of Sickle Cell Disease Gene Therapies on State Medicaid Programs

Harvey JP, Raymakers AJN, Rand LZG, Goshua G, Kesselheim AS, Pandya A - Journal of General Internal Medicine

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
New gene therapies for sickle cell disease could increase state Medicaid budgets by an estimated $837.5 million over five years, highliging the need for novel policy interventions and payment mechanisms, such as the CMS Cell and Gene Therapy Access Model, to control costs while maintaining patient access.
View Source

Overlapping Method of Use Patents to Prevent Generic Entry

Park J, Kesselheim AS, Tu SS - Journal of Law, Medicine & Ethics

  • Innovation Incentives and Competition
Talk bubble graphics representing commentary and opinion.
Brand-name pharmaceutical companies increasingly use overlapping patents and FDA use codes to delay the generic entry. This study uses two recent cases, icosapent ethyl (Vascepa) and sacubitril-valsartan (Entresto), to show how these tactics can obstruct the skinny labeling pathway for generic products. To restore balance between exclusivity and competition in the US pharmaceutical market, reforms to use codes and the legal standards for patent ingringement are necessary.
View Source

Breakthrough Therapy Designations in China and the United States

Mao X, Li Y, Kesselheim AS, Ba Y, Li G - Nature Reviews Drug Discovery

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Since 2020, the Chinese NMPA received nearly twice as many breakthrough therapy designation (BTD) applications for drugs as the FDA, but granted a lower percentage than the US regulator. Most BTDs in China were for domestically developed drugs, and oncology led BTD approvals in both countries. As use of the BTD pathway continues, both countries should create clear, rigorous evaluation criteria to ensure the pathway prioritizes truly promising new therapies.
View Source

PORTAL Post | August-September 2025

  • Innovation Incentives and Competition
  • Price, Value, and Access
  • Regulation and Clinical Evidence
A graphic icon of a megaphone as a symbol for the PORTAL Post email newsletter.
The August-September 2025 edition of the PORTAL Post monthly newsletter.
View Source

Medicare Part D Savings Under the Manufacturer Discount Program vs Coverage Gap Discounts

Rome BN, Garrett KR, Maini L - JAMA Network Open

  • Price, Value, and Access
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
When comparing the Coverage Gap Discount (CGD) and the Manufacturer Discount Program (MDP) in Medicare Part D, Medicare would have received $34 billion from drug makers under the MDP, compared to $17 billion under the CGD based on 2022 data. Discounts in the MDP also increased substantially for high-cost specialty drugs, highlighting how this policy change will affect Medicare Part D spending going forward.
View Source

Bridging the Fair Share Gap for Antibacterial Innovation: an Observational Analysis of Antibacterial Revenues in the G7 and EU27

Goh M, McEnany M, Freeman R, Newton M, Kesselheim AS, Outterson K - eClinicalMedicine

  • Price, Value, and Access
  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Among high-income countries, the G7 and EU countries fall short of revenue targets needed to sustain research for new antibiotic development, with the UK and Italy as notable exceptions. Revenue guarantee incentives could help bridge gaps in antibiotic investment in wealthier countries amid a growing threat of antimicrobial resistance.
View Source

Physician Perspectives on Pharmaceutical Promotion

Mooney H, Austad KE, Campbell EG, Avorn J, Lu Z, Kesselheim AS - JAMA Health Forum

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
Physicians surveyed in 2011 and 2024 increasingly recognized the value of the materials they receive from drug companies, but remained concerned about the impact on public trust in medicine. To address these concerns, professional societies, payers, and regulators should collaborate to create unbiased educational resources for clinicians on the efficacy and safety of drugs.
View Source

Lowering Drug Prices in the US-Look Within, Not Abroad

Gondi S, Papanicolas I, Rome BN - JAMA

  • Price, Value, and Access
Talk bubble graphics representing commentary and opinion.
The authors outline the limitations of benchmarking US drug prices to those abroad via international reference pricing, recommending instead that the US adopt transparent, evidence-based health technology assessment and negotiation processes to address high drug costs.
View Source

Trends in Time to Withdrawal and Full Approval of Accelerated Approval Cancer Drug Indications (1992-2024)

Jenei K, Hahn G, Kesselheim AS, Tibau Martorell A - Journal of Cancer Policy

  • Regulation and Clinical Evidence
Simple graphic of magnifying glass examining papers to signify reviewing research publications.
The median time from FDA accelerated approval to full approval for cancer drugs decreased from 4.3 years in 1992 to 2.3 years in 2025, with a reduction in median withdrawal time from 9.5 to 3.2 years. The proportion of confirmatory studies underway at approval rose from 63% to 85% during this period. These findings may reflect improved regulatory oversight or more flexible approval, highlighting the need for timely, clinically meaningful confirmatory evidence to ensure real patient benefit and reduce uncertainty.
View Source